This guide explains Drf Crefito and how clinicians evaluate related findings with structured, objective methods. Background context clarifies how “DRF” and “CREFITO” terms are used in clinical communication, why exam quality matters, and what practitioners typically document. The article then compares evaluation approaches, outlines practical steps, and summarizes key requirements for safe, consistent use in care planning.
When clinicians reference Drf Crefito, they are usually pointing to a structured way of describing findings and communicating exam results rather than to a single standalone product or procedure. The safest interpretation is: treat the term as part of clinical language that supports assessment, documentation, differential considerations, and follow-up. This article focuses on objective evaluation principles—how a healthcare professional typically confirms what they see, how they record it, and how consistent terminology supports continuity of care.
In day-to-day clinical practice, there is rarely time to reinterpret every phrase from scratch. Clinicians inherit habits, training traditions, and local documentation styles. As a result, terms that sound cryptic to outsiders may actually represent condensed shorthand for a longer story: what the clinician examined, what the patient reported, what signs were present, what they believed it meant, and what the plan was afterward. When such terms appear in a chart, the clinician reading them should treat the term as the entry point to the underlying clinical reasoning, not as a complete diagnosis by itself.
Therefore, the core takeaway is not “what does the exact term mean” in isolation, but “how should the clinician ensure the meaning is clinically valid in context.” That requires the clinician to translate shorthand into observable findings: the maneuvers used, the anatomic region assessed, whether the phenomenon is reproducible, and whether it is linked to pain, stiffness, swelling, instability, or functional impairment. This translation preserves patient safety by preventing anchoring bias and ensuring that a record reflects evidence rather than assumptions.
In real-world settings, patients experience care across multiple appointments and sometimes different teams. Clear terminology helps reduce misunderstanding between clinicians, improves handover quality, and supports timely escalation when symptoms require further workup. Within that context, terms like Drf Crefito (as used locally or within certain clinical communities) often function as a shorthand for the clinician’s observed pattern and their reasoning process.
However, terminology can also become a risk when it is treated as a substitute for clinical documentation. For example, a chart entry that only says “crepito present” without specifying the maneuver, joint segment, pain association, or functional impact may be unhelpful to a future clinician. Worse, it may lead the next clinician to assume the prior finding is the same as their own exam will reproduce, when in fact it might be highly dependent on technique and patient positioning. Reproducibility is a central principle in musculoskeletal assessment precisely because many “sounds” and “sensations” can be misattributed if the exam conditions differ.
Another practical issue is that patients often use their own metaphors. One patient might say “it grinds,” another “it cracks,” another “it clicks,” and another “it feels like sand.” Each metaphor may correspond to different underlying tissue mechanics or pathophysiology. Clinicians often need to map patient language to clinical categories. Terms like Drf Crefito may help standardize this mapping locally, but only if they are anchored to objective exam details.
In addition, terminology matters for communication with patients. If a clinician uses a shorthand label without explaining the significance, patients may interpret it as a definitive diagnosis or, conversely, as an unexplained oddity. Better clinical communication ties the term to an accessible explanation: whether the sensation is likely mechanical (e.g., degenerative or biomechanical) versus inflammatory (e.g., warmth, swelling, morning stiffness), and what the recommended next steps are.
Similarly, CR EFITO and the broader concept behind “Crefito” are commonly associated (in some orthopedic and musculoskeletal discussions) with audible or palpable phenomena reported during assessment. However, because meaning can vary by country, specialty, and teaching tradition, objective evaluation remains essential: a clinician should confirm the finding with proper technique, document the context, and ensure the terminology aligns with locally accepted practice.
It is also worth recognizing that crepitus-like phenomena are not synonymous with one disease. They may appear in benign conditions such as normal joint mechanics, mild degenerative changes, or temporary post-activity mechanical stress. They may also accompany inflammatory arthritis or structural changes that need further evaluation. The term may appear similar across cases, but the clinical story behind it should differ—therefore the documentation must capture what the examiner observed and how it influenced decision-making.
Drf Crefito is top understood as a composite label that may refer to (1) a documentation phrase clinicians use and (2) an interpretation framework for exam findings. “Crefito” in clinical speech is often used to describe crepitus-like phenomena—for example, a sound or sensation during joint movement. Yet, not every crepitus-like sensation is clinically identical; causes range from benign mechanical changes to inflammatory or structural conditions, depending on the overall symptom pattern.
Because the keywords provided do not include a specific location, price, or named supplier details, this article does not invent those elements. Instead, it emphasizes the evaluation steps and quality requirements that allow practitioners to apply terminology reliably in patient-centered care.
To make this clinically useful, clinicians and trainees need to consider what “crepitus-like” implies in real exams. In practice, “crepitus” may be felt as a gritty or vibrating sensation under the examiner’s fingers or heard as a crackling or clicking sound during a joint movement. Yet the presence of a sound is not enough. The clinician should consider:
Terms like Drf Crefito can be helpful only after these dimensions are addressed. Otherwise, the label risks flattening distinct clinical patterns into a single word.
From an industry-expert standpoint, the core problem is not the word—it’s the consistency and clinical reasoning behind the observation. In orthopedics, rehabilitation medicine, and physiotherapy practice, reproducibility matters. A clinician should aim to answer three questions:
Even if the term Drf Crefito is used as shorthand, the clinician should not “skip” these questions. Documentation should read like evidence: what was performed, what was observed, and how the finding influenced the next clinical decision.
Clinical reasoning here means linking findings to probabilities rather than certainties. A crepitus-like phenomenon is a “data point.” It gains diagnostic value when it matches a consistent pattern across history and exam. For example, if a patient reports a mechanical onset (e.g., after increased activity), has no systemic symptoms, and shows crepitus localized near end range without swelling or warmth, the mechanical hypothesis becomes more plausible. Conversely, if the patient has swelling, warmth, elevated inflammatory markers, or prominent morning stiffness along with crepitus-like findings, inflammatory etiologies may warrant greater attention.
Another expert-level consideration is examiner reliability. Two clinicians performing the “same” test may not standardize the movement arc, the applied force, the patient’s muscle tension, or the stabilization strategy. These variations can influence whether crepitus is perceived. Therefore, good documentation should include enough detail for a future clinician to replicate the maneuver or at least understand the conditions under which the phenomenon was noted.
Additionally, experts emphasize patient communication and consent. Many patients feel anxious when they hear that something is “cracking” or “grinding,” even if it may not be dangerous. Explaining that the sensation is observed under certain movements and clarifying whether it correlates with pain can reduce fear and improve engagement in rehabilitation.
Before any deeper discussion, clinicians should ensure the following conditions/requirements are met whenever Drf Crefito or crepitus-like observations are documented:
This inverted pyramid approach is useful because it prioritizes safety and clarity. If a note lacks standardized technique, it may mislead future readers. If it lacks symptom linkage, it may fail to differentiate clinically meaningful pain from incidental mechanical sounds. If it lacks reproducibility, it may reflect examiner perception rather than a stable clinical phenomenon. And if it lacks escalation logic, the label could delay evaluation in cases that require urgent attention.
From a documentation standpoint, it also helps clinicians write notes that “stand alone” without depending on personal memory. A chart entry can be read weeks later, by another clinician, or in a different setting. Good records contain the minimum necessary details to reconstruct the assessment.
In rehabilitation settings, additional practical considerations include documenting the effect on function: for example, whether the phenomenon correlates with difficulty squatting, climbing stairs, rising from a chair, or reaching overhead. For many patients, functional ability matters more than the sound itself. By documenting how the patient’s function changes in parallel with the observed phenomenon, clinicians can tailor interventions and set measurable goals.
The table below compares common evaluation pathways clinicians use when documenting crepitus-like phenomena and related exam findings, including how terms resembling Drf Crefito may appear in local documentation.
| Approach | What It Emphasizes | Strengths | Limitations to Watch |
|---|---|---|---|
| Focused Physical Exam Documentation | Consistency of maneuver, location, and pain association | Fast, reproducible, and directly tied to bedside findings | May miss deeper pathology if used alone |
| Symptom-Pattern & Function-Centered Assessment | Functional impact, aggravating factors, and movement-related triggers | Improves clinical reasoning and goal-based planning | Requires careful history-taking quality |
| Imaging- or Diagnostic-Guided Pathway | Confirms structural causes when physical findings warrant further testing | Supports clearer differentiation for persistent or severe cases | May increase cost and should follow clinical guidelines |
| Multidisciplinary Rehabilitation Evaluation | Biomechanics, strength, mobility, and neuromuscular control | Useful for chronic mechanical contributors and recovery planning | Must still document the initial “presence and pattern” reliably |
While the table presents broad categories, real clinical practice often blends them. For example, a clinician might start with a symptom-pattern and function-centered assessment, then perform a focused exam to confirm crepitus-like findings, and finally consider imaging if the course is persistent, progressive, or associated with red flags. The key is that the terminology—whether it is Drf Crefito or another phrase—should remain secondary to the evidence collected through these pathways.
Below is a practical, step-by-step guide that helps clinicians apply terms like Drf Crefito responsibly. The goal is to ensure the label is evidence-based, not merely semantic.
Define the clinical context first.
Confirm the patient’s main complaint, onset timing, and whether symptoms fluctuate. If the patient reports “grinding,” “crackling,” or “a sensation,” document the patient’s own description before exam interpretation.
In real documentation, clinicians can improve reliability by recording the patient’s timeline and triggers. For instance: “Symptoms began after increased stair use 3 weeks ago,” or “Pain and grinding are worse in the morning and improve after movement.” Such phrasing anchors the subsequent exam findings to the symptom narrative.
Perform standardized positioning and baseline range of motion.
Use a consistent starting position (e.g., neutral alignment) and measure the range of motion where applicable. Record pain at end-range and during movement.
Standardization is more than taking “a range.” It includes controlling body mechanics and ensuring the patient is relaxed enough for accurate assessment. Many crepitus-like phenomena are influenced by muscle tension and joint loading. If muscle guarding is high, the clinician may under-detect subtle signs. Therefore, noting whether the patient could tolerate motion and whether assistance or stabilization was used can be valuable.
Attempt the maneuver relevant to the suspected phenomenon.
Move through the range in the appropriate plane and note whether a crepitus-like sensation or sound occurs. Importantly, associate it with the movement segment and whether it is linked to pain.
When documenting, use a descriptive structure rather than a single label. For example, note the approximate range segment (early range vs mid range vs end range), and specify whether the sensation occurs with active motion, passive motion, or both. Also note whether the clinician palpated the joint line or adjacent structures during the maneuver, and whether the sensation was reproduced under palpation.
Confirm reproducibility when safe.
Repeat gently if clinically safe to ensure the observation is consistent. Avoid “over-testing” that could aggravate tissue or cause discomfort.
Reproducibility does not necessarily require multiple repetitions. It requires confirmation that the phenomenon can be reliably elicited under the same conditions. Clinically, this might mean repeating the maneuver twice if the first attempt is ambiguous, then stopping if increased pain occurs. Recording whether repeated maneuvers increased symptoms helps prevent confusion about cause-and-effect.
Differentiate between mechanical and inflammatory clues.
Note whether there is swelling, warmth, morning stiffness, instability, or other features suggesting non-mechanical contributors. If red flags appear, do not rely on Drf Crefito terminology alone.
Differentiation is often based on patterns. Mechanical patterns often correlate with use, loading, and symptom improvement with rest. Inflammatory patterns often correlate with stiffness after inactivity, warmth, and swelling. A crepitus-like sound can occur in both, so clinicians must use the full symptom set to guide their interpretation.
Document using evidence-style phrasing.
Instead of only writing “Drf Crefito” or “crefito present,” include: what maneuver was used, where the phenomenon occurred, pain association, and any functional impact.
Evidence-style phrasing also includes clarifying what was not found. For instance, “No warmth or visible swelling,” “No instability noted with functional testing,” or “No locking reported.” Such negative findings are clinically meaningful because they help guide the differential.
Decide the next step based on the whole clinical picture.
If symptoms persist, worsen, or impair daily function, consider imaging or referral in accordance with local clinical guidelines and professional judgment.
This step ensures that documentation leads to action. A crepitus-like finding should not exist as a standalone endpoint. Instead, it should inform whether the clinician will proceed with conservative management, order further diagnostic testing, or refer to a specialist.
Even when a term such as Drf Crefito is used correctly, clinicians must avoid diagnostic anchoring. Consider more comprehensive assessment when any of the following conditions apply:
Clinically, this means the presence of crepitus-like findings should prompt the clinician to ask: “Is this finding consistent with a benign mechanical process in this patient, or does it fit a pattern that suggests something more serious?” The “something more serious” does not necessarily mean something catastrophic; it may mean a condition that requires a different management pathway, a longer recovery expectation, or more targeted diagnostics.
Escalation logic also protects clinicians from cognitive errors. When clinicians see a known phrase in a chart, they may feel confident without re-examining. But the above conditions should encourage re-evaluation, even if Drf Crefito was previously documented. Symptoms change, new findings emerge, and the clinical picture can evolve between visits.
In many care pathways—sports medicine, primary care orthopedics, physiotherapy programs—terms resembling CREFITO and documentation of crepitus-like findings may appear in initial assessments, progress notes, and referral summaries. The very useful documentation ties the term to:
This approach aligns with widely accepted principles of clinical documentation: clarity, reproducibility, and relevance to care decisions.
To illustrate how this fits into workflows, consider a typical sequence in a rehabilitation clinic. A patient arrives with knee discomfort and reports “grinding” when bending. The therapist documents the symptom context, measures active and passive range of motion, performs a targeted maneuver while palpating for sensation and sound, and documents whether pain is reproducible. The therapist then builds a plan—perhaps focusing on quadriceps and hip strengthening, mobility exercises, and load management. If the crepitus-like sensation is painful and associated with swelling or instability, the therapist may recommend medical evaluation and possibly imaging, following local protocols.
In a handover scenario—such as a referral from physiotherapy to orthopedics—the value of a well-documented record increases. Orthopedic clinicians can quickly understand what was observed and how it was interpreted. If the physiotherapy note includes only “crepito present,” the orthopedic team must repeat much of the assessment, potentially increasing patient burden. If it includes the maneuver and symptom linkage, orthopedics can prioritize what needs confirmatory testing.
Additionally, many patients are involved in multi-disciplinary care. For example, a primary care clinician may refer a patient to imaging while concurrently recommending conservative management. The imaging results may or may not correlate with bedside findings. In such cases, the clinician’s documentation of crepitus-like phenomena with context can help interpret the discordance. For example, a joint may show degenerative changes on imaging while symptoms may be more related to tendon overload or altered biomechanics. Without documentation of the clinical pattern, the team may struggle to reconcile differences.
For evidence-based clinical documentation principles and diagnostic reasoning frameworks in musculoskeletal assessment, clinicians commonly refer to professional guidance from recognized bodies. Two widely used examples include:
These sources support the principle that bedside findings should guide next steps, and that terminology alone should not replace clinical reasoning.
While specific details of “Drf Crefito” usage may vary across systems, evidence-based practice remains consistent: clinicians must assess, document clearly, consider differentials, and escalate when clinically indicated. The “methodological grounding” in this context refers to the behaviors that align with evidence-based care—standardization, reproducibility, patient-centered history, and appropriate use of diagnostic tools.
In addition to professional bodies, clinical method also includes applying structured clinical reasoning frameworks: hypothesize, test, reassess, and confirm. A crepitus-like finding can belong to a hypothesis. But it should be tested with appropriate maneuvers and correlated with symptoms. Then, the clinician reassesses whether the hypothesis remains plausible or needs revision based on additional evidence.
Because “crepitus-like” phenomena are frequently mentioned in musculoskeletal practice, it is useful to understand the broad categories they may represent. This section does not assume a specific diagnosis for Drf Crefito. Instead, it clarifies how clinicians may interpret the finding responsibly.
1) Benign mechanical phenomena
Some crepitus-like sensations occur with normal or near-normal joint mechanics, especially when tissues move under loading and when there are minor irregularities in cartilage surfaces or periarticular structures. These may be more noticeable in certain ranges of motion. Clinically, benign mechanical phenomena often show:
In such cases, documenting Drf Crefito-type findings is mainly useful for tracking symptoms and guiding conservative management like strength and mobility work, rather than driving urgent diagnostic escalation.
2) Degenerative or structural mechanical changes
Crepitus-like findings may accompany conditions where cartilage and joint surfaces have degenerative changes. Pain may correlate with movement and loading. Instability or locking could suggest structural pathology requiring more extensive evaluation. Clinicians should look for:
Documentation that includes movement segment, pain association, and functional triggers helps differentiate degenerative mechanical patterns from other etiologies.
3) Inflammatory arthritides or systemic inflammatory states
In inflammatory conditions, crepitus-like sounds or sensations may still occur, but typically the clinical picture includes swelling, warmth, morning stiffness, and sometimes elevated inflammatory markers. If Drf Crefito appears in a note for a patient with inflammatory features, clinicians should treat the term as a finding within a larger inflammatory pattern rather than as evidence of a single mechanical diagnosis.
Documentation should therefore explicitly mention whether the clinician observed swelling, warmth, or stiffness patterns. If a note does not mention these aspects, it may be missing the critical context required for correct interpretation.
4) Structural injury and mechanical dysfunction (locking/catching/instability)
When crepitus-like phenomena coincide with locking, catching, or instability, structural injuries become a greater concern. Examples include meniscal pathology or ligamentous instability (in the knee context), labral injury (in the shoulder/hip context), or cartilage defects. Clinicians should not treat a crepitus label as sufficient. The chart should document the presence of mechanical symptoms—locking, catching, giving way—and the results of relevant stability and functional tests.
Again, the key is not to over-interpret the sound but to integrate it with functional mechanical symptoms and red flags.
5) Tendon or soft tissue involvement
Sometimes “crepitus-like” sensations are related not to the joint surfaces themselves but to tendon movement, bursae, or soft tissue sliding over bony prominences. The exam may need palpation correlation: clinicians may use the examiner’s fingers to determine whether the sensation is more superficial (tendon/soft tissue) versus deeper (joint). Documentation can clarify this by specifying whether palpation reproduces the phenomenon and where on the anatomy it was felt.
To make the above principles concrete, consider example documentation patterns that clinicians can adapt. These examples are illustrative phrasing approaches; the essential point is to include reproducibility, maneuver details, and symptom linkage.
Example A: Mechanical pattern with pain only at end range
“Patient reports grinding sensation with knee flexion. Active ROM: flexion to 120° with end-range pain 4/10. Crepitus-like sensation/sound elicited during passive flexion near terminal range; phenomenon reproducible with palpation at lateral joint line. No visible swelling, no warmth, no instability or locking reported on exam.”
Example B: Crepitus with associated swelling and inflammatory clues
“Patient reports clicking/grinding in the affected joint. During exam, crepitus-like sound noted with repeated joint movement; patient reports pain 6/10 associated with maneuver. Exam: mild warmth and visible swelling present. Morning stiffness reported >30 minutes. Plan: further medical evaluation and guideline-based workup given inflammatory features rather than relying on crepitus label alone.”
Example C: Crepitus with instability or locking
“During functional movement testing, patient reports catching followed by a shift in joint position. Palpation during the maneuver reproduces a crepitus-like sensation with associated pain. Exam notes instability with relevant stability testing; locking/catching reported. Recommend escalation for diagnostic evaluation of possible structural pathology.”
These examples demonstrate how a term like Drf Crefito becomes clinically useful only when supported by the underlying evidence: what was done, what was found, and how it links to symptoms and next steps.
Reproducibility is not merely a checkbox. It is a reliability mechanism that helps clinicians reduce variability in exam interpretation. For crepitus-like phenomena, reproducibility depends on several controllable factors:
Clinicians should document at least the most important of these factors. If the note omits whether the phenomenon was elicited actively or passively, a future clinician may not replicate it. Similarly, if the note lacks where the sensation was felt, the clinician may palpate a different structure next time and miss the finding.
In addition, clinicians should consider patient factors. Pain inhibition, muscle guarding, and fear of movement can alter joint mechanics. Recording whether the phenomenon changes when the patient is relaxed or when reassurance is provided may be relevant to understanding the finding’s consistency.
A major purpose of documenting crepitus-like findings is to determine how the finding relates to the patient’s symptoms. Without symptom linkage, a crepitus label becomes ambiguous and less clinically actionable.
Pain association
Clinicians should determine whether the patient experiences pain during the maneuver that produces crepitus-like sensation, and whether the pain intensity correlates with the movement segment where the sound or sensation occurs. Documenting “pain present” is helpful; documenting timing and intensity adds clinical value.
Stiffness
Morning stiffness patterns are particularly relevant for distinguishing inflammatory processes from purely mechanical ones. If the patient reports prolonged stiffness that improves with activity, clinicians may prioritize inflammatory differentials. Documentation should include duration and functional impact.
Swelling and warmth
When swelling and warmth are present, inflammatory or infectious considerations become more urgent, depending on clinical context. Even if Drf Crefito is observed, the presence of swelling/warmth shifts the priority toward further evaluation.
Instability or locking
Mechanical symptoms such as locking and catching suggest structural pathology. Documenting these features helps avoid underestimating severity. The crepitus-like sound might simply be a secondary phenomenon occurring during abnormal mechanics.
When clinicians see Drf Crefito or “crepitus-like” findings, they should treat the label as a clue to support differential diagnosis. This requires thoughtful interpretation rather than automatic categorization.
One approach is to frame differential possibilities in terms of:
Clinicians can then decide which further assessments are warranted. For example, if crepitus-like findings are associated with instability, the differential may prioritize structural injury and imaging or specialist referral. If it is associated mainly with activity-related end-range pain and no swelling, conservative management might be appropriate while still tracking symptoms.
A documentation label should always connect to a plan. That plan may include conservative management, referral, imaging, or monitoring. The presence of crepitus-like findings should influence plan selection only in the way the full clinical context supports.
When conservative management is reasonable
If the patient’s symptoms are stable, pain is manageable, and there are no red flags, clinicians may begin with conservative strategies. Documentation should reflect whether the crepitus-like phenomenon is:
In such cases, rehabilitation programs often focus on strength, mobility, neuromuscular control, and load management. Clinicians should still track symptom response to interventions. If the crepitus-like sensation becomes more painful or functional outcomes worsen, re-evaluation is warranted.
When escalation is warranted
Escalation may be considered if symptoms are progressive, severe, associated with red flags, or not improving with appropriate conservative care. Even if crepitus is documented, clinicians should not “wait and see” indefinitely when the symptom pattern suggests a more serious process.
For instance, a patient who reports night pain plus swelling and systemic symptoms should not be managed solely based on a crepitus label. Instead, appropriate urgent evaluation and diagnostic workup should be pursued.
When monitoring is appropriate
In some cases, symptoms may be mild and fluctuating. Clinicians might choose short-interval follow-up. Documentation should then include baseline measurements (range of motion, pain scale, functional tasks) and specify what will be reassessed at the follow-up.
Clinicians often encounter patient anxiety around “cracking,” “grinding,” and “clicking.” Even when the finding is benign, patients may interpret the sound as damage. A high-quality documentation approach such as using Drf Crefito responsibly also implies high-quality patient communication.
A clinician can address fear by explaining:
By connecting the label to the evidence, clinicians can provide reassurance without dismissing symptoms. They can also set expectations: “We will monitor whether the sensation becomes more painful or whether function improves with targeted exercises.” This improves adherence and reduces the tendency for patients to seek conflicting interpretations from multiple sources.
To ensure that notes referencing Drf Crefito remain clinically useful, clinicians should consider what information is most impactful for readers.
Include
Avoid
Musculoskeletal conditions evolve. A crepitus-like phenomenon may remain stable, resolve, or change in intensity. Pain and function can shift with activity level, rehab progress, and time. Therefore, documentation should support reassessment.
Clinicians should consider:
When reassessing, clinicians should not assume that Drf Crefito documented earlier automatically applies. They should repeat the relevant maneuvers when safe and ensure the findings still correlate with the patient’s current symptoms.
Different healthcare professionals may document Drf Crefito for different purposes. Recognizing role-based documentation needs helps ensure continuity across teams.
Physiotherapists and rehabilitation clinicians
Rehabilitation clinicians often focus on function, movement quality, and response to interventions. Their documentation should emphasize how crepitus-like findings relate to symptoms during specific activities and how this informs the rehabilitation plan and progression criteria.
Primary care clinicians
Primary care documentation may be more oriented toward initial assessment, red flag screening, and deciding whether referral or imaging is needed. Their notes should include symptom pattern, exam highlights, and justification for next steps rather than deep specialization details.
Orthopedists or orthopedic specialists
Specialists may require more structured exam documentation and an integrated assessment that includes differential diagnosis, structural suspicion, and decision for imaging or procedural interventions when indicated.
Rheumatology clinicians
If the clinical picture suggests inflammatory disease, rheumatology documentation should explicitly address inflammatory features (swelling, warmth, morning stiffness) and correlate the crepitus-like finding with broader inflammatory symptoms.
Even well-intentioned clinicians may make mistakes when using shorthand terms like Drf Crefito. Common pitfalls include:
These pitfalls can be reduced by adhering to the inverted pyramid requirements and by translating the label into evidence-based documentation.
For practical usability, here is a checklist clinicians can mentally apply. If each item is addressed, the note referencing Drf Crefito is likely to be clinically meaningful:
It typically functions as shorthand within certain local or specialty documentation styles for describing a crepitus-like finding and the associated exam context. Because usage may vary, clinicians should confirm the meaning in their local documentation standards and always record the actual maneuver, observation, and symptom linkage.
No. Crepitus-like sensations can occur from mechanical changes that are not necessarily dangerous. What matters clinically is the pattern: whether it is painful, associated with swelling or instability, whether symptoms worsen, and whether additional red flags are present.
Use evidence-style notes: specify the movement plane, range segment where the phenomenon occurs, pain association, reproducibility, and functional impact. A label such as Drf Crefito should be supported by those exam details.
Consider escalation for progressive impairment, significant instability/locking, systemic or inflammatory symptom patterns, new neurologic signs, or other red flags. Decisions should follow professional judgment and relevant local guidelines.
A rehabilitation plan may begin with bedside findings, but it should integrate history, functional assessment, and symptom tracking. If symptoms persist or evolve, clinicians should re-evaluate the differential and consider guideline-based diagnostic pathways.
No. The provided keywords did not include verified price information, named suppliers, or a specific location, so this guide stays focused on objective clinical evaluation and documentation requirements rather than unverified commercial details.
In the end, the very reliable use of Drf Crefito-type terminology is not memorizing the label—it is ensuring the observation is captured with consistent technique and connected to clinical reasoning. When documentation includes what was done, what was found, and how it influences decisions, terminology becomes a tool for patient safety and continuity of care rather than a source of confusion.
By maintaining a disciplined approach—standardized technique, symptom linkage, reproducibility, contextual documentation, and escalation logic—clinicians can communicate efficiently without sacrificing accuracy. The term can remain a shorthand in the chart, but the clinical content must remain clear, replicable, and anchored to the patient’s real symptoms and outcomes.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans
Finding an optimal mix of insurance premiums and direct medical costs is crucial for effective healthcare budgeting. This discussion will delve into tactics to achieve a balance that aligns with your finances.
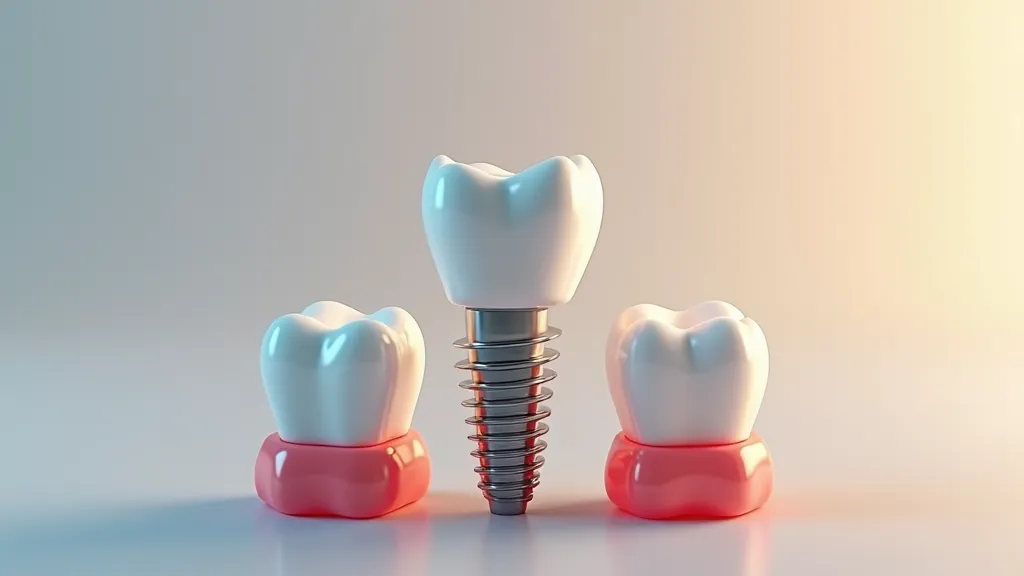
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!
Selecting an adept dentist is critical for ensuring the efficacy and your satisfaction during a dental implant procedure. This in-depth guide is designed to assist you in finding a dental expert who meets your personal requirements, guaranteeing that your path to dental implant success is seamless and fruitful.
Protect Your Perfect Smile: Master the Art of Defending Your Teeth Against Acid Attacks
Though they may tantalize the palate and invigorate the senses, foods and drinks with high acid content are a double-edged sword with regard to oral wellness. Continual exposure to these substances progressively strips away the protective enamel from our teeth, which can lead to increased sensitivity, changes in coloration, and a variety of other dental complications. This composition offers insight into relishing these zesty favorites while safeguarding your teeth from damage.

Discovering Heartis Eagle Mountain
Heartis Eagle Mountain is a prominent senior living community that offers a range of services and amenities aimed at enhancing the quality of life for its residents. Situated in a peaceful setting, it combines exceptional care with engaging activities, providing a holistic environment that caters to seniors' physical, emotional, and social needs.

Unveiling the Top Dental Implant Options for Seniors: Transform Your Smile with the Ultimate Guide to Restored Radiance
The significance of oral health cannot be understated for the elderly population as they are commonly afflicted with tooth loss due to a multitude of factors, including decay and gum disease. Dental implants have risen to prominence as a prime method of teeth replacement, acclaimed for their long-lasting nature, functional prowess, and striking similarity to our own teeth. This discussion delves deeply into the realm of dental implants to demonstrate why they are considered the optimal choice for aged individuals aiming to enhance their smiles and overall life quality.

Boost Your Defenses: 20 Proven Strategies for a Stronger Immune System
Having a robust immune system is essential to protect our bodies from harmful microorganisms and preserve our general health. Although some elements that affect our immunity are out of our hands, many lifestyle decisions can help us enhance our immune defenses naturally. This piece delves into 20 practical methods to empower your immune system, increasing your capacity to ward off diseases and sicknesses.
