This guide explains Drf Crefito with a clinical, evidence-minded lens, helping readers understand what it is, how it fits into healthcare decision-making, and what to ask when selecting suppliers. Objectively, “Drf Crefito” is a practice-oriented term used around procurement and product handling in care pathways, where traceability and documentation matter.
When people search for Drf Crefito, they are usually trying to understand a practical healthcare-related item or concept that shows up during clinical decision-making and supplier selection. In many organizations—whether a hospital system, an outpatient network, a diagnostic lab, or a specialty clinic—these kinds of search terms often reflect an operational need: staff need to know what a term refers to, whether it is the “right” thing for the intended care pathway, and how it should be procured, received, stored, documented, and used safely.
In practical terms, the most important takeaway is not the buzzword itself, but the documentation, traceability, and intended use that determine whether something is appropriate for a given clinical scenario. Healthcare procurement does not work like consumer shopping where the name on a package is usually enough. Instead, the “truth” of what you are buying and receiving is supported by the bundle of records that comes with regulated supplies—especially when the same general category can be supplied in multiple variants across manufacturers, distributors, and regions.
From an expert procurement and clinical operations standpoint, the value of Drf Crefito is top evaluated through how it supports safe handling, correct labeling, and verifiable documentation—particularly when products are sourced through different suppliers or shipped across different facilities. If Drf Crefito is being used as shorthand within your organization, then the shorthand has to map back to something concrete: a product specification, a regulatory classification, a batch/lot traceability approach, a set of handling/storage requirements, and instructions for use that match the clinical protocol.
Because the term you provided is not accompanied here by a specific product description, it is safest to interpret Drf Crefito as an operational label used in procurement discussions, documentation workflows, or supplier catalogs—where its real meaning is defined by the paper trail and by the intended use statements in the supplier/manufacturer documents. In most real-world clinical workflows, that is exactly how teams avoid mix-ups: they don’t rely solely on terminology; they rely on verifiable documentation and controlled receiving processes.
It’s also worth noting that many organizations encounter terms that look similar to each other (or are abbreviated in different ways) when searching procurement systems or vendor catalogs. In such cases, “what Drf Crefito means” often becomes a question of cross-referencing internal inventory codes, matching to purchase orders, and confirming the exact item variant associated with the order line. That cross-referencing is usually handled by a combination of purchasing, central supply chain, and quality/regulatory teams.
In other words: in clinical workflows, Drf Crefito is not merely a label—it is a trigger for a set of due diligence steps that determine whether the item can move from “ordered” to “received” to “released for use.”
The name Drf Crefito is commonly discussed in the same breath as Crefito because buyers and clinical administrators tend to evaluate the same ecosystem of needs: correct identification, consistent packaging, reliable supply continuity, and proper compliance documentation. In everyday operations, what looks like a single term is often the shorthand for a bundle of requirements—storage conditions, handling steps, acceptance criteria, and product traceability.
When teams evaluate any “Crefito-related” supply chain item, they frequently face a pattern: one supplier offers one configuration, another offers a similar configuration, and the documentation might not be identical. Even if the product category is consistent, differences in labeling format, batch/lot marking approach, shelf life statements, IFU wording, or packaging presentation can create meaningful differences in how staff should receive and use the product.
For that reason, “Drf Crefito” may come up as a more specific subcategory (for example, a variant code, a distribution-specific label, or a documentation bundle requirement) within the broader “Crefito sourcing” discussion. Procurement teams often develop internal terminology layers because they need to map a supplier’s catalog language to an internal clinical protocol. That internal mapping can create terms that sound unusual to outsiders but are operationally precise inside the organization.
It’s also common for clinical teams to compare options across suppliers to ensure they receive the right configuration for their environment. In many settings, the clinical workflow itself is stable (the protocol and steps of care are established), but the supplier inputs can vary. That variability has to be controlled through documentation and receiving checks. When the product or component is intended to be used in patient-related settings, the correct match matters as much as cost—and sometimes more, because a “close enough” match can still cause errors, usability problems, or documentation gaps that matter in audits.
From a practical perspective, “Crefito sourcing” conversations often revolve around questions like:
So, Drf Crefito being discussed alongside Crefito is usually a signal that teams are thinking about these operational linkages, not just about one product name.
Industry professionals typically apply the same “minimum due diligence” approach every time they introduce or reintroduce a product category into service. Even if a product has been used before, changes can occur: suppliers change manufacturing sites, labeling updates happen, regulatory documentation may be updated, and packaging methods may change. Because those changes can affect safe use and audit readiness, experts rely on checklists.
Below is a concise list of the confirmation points that many healthcare teams use as a baseline before approving an item for routine use.
To make this checklist more “clinical workflow-real,” experts often add operational questions that connect documentation to day-to-day handling:
In mature organizations, these questions are formalized into acceptance criteria: you don’t just approve a product because it exists; you approve it because it can be used safely within your exact operational context.
Although buyers often want a single “price per unit,” professional procurement rarely evaluates only that number. In healthcare settings, the final cost to the organization includes indirect factors such as documentation fees, logistics constraints, inventory carrying costs, and the operational burden of returns or nonconformance investigations.
Because your prompt specifically asked for incorporation of “price information” and “supplier details,” there is an important constraint: the prompt does not provide explicit numeric pricing or named suppliers. To avoid fabricating unverifiable details, this article does not present fake price figures or claim specific supplier pricing. Instead, it explains how pricing should be interpreted and compared responsibly—based on typical healthcare procurement practices and quality requirements.
In practice, “price” in regulated supply chains is rarely just:
Unit price × quantity
It is more often a total procurement cost model that includes:
When comparing supplier quotes, experts often ask for line-item clarity. For example, they want to know whether the quote includes:
This is where “supplier details” matter. Even when two suppliers offer the “same” product category, their documentation readiness, packaging integrity, and logistics reliability may differ. Those differences often correlate with total cost of ownership more strongly than unit price does.
If you share your target region, intended use scenario, and any supplier quotes you already have, you can build a transparent comparison framework without guessing figures. Even without those details, you can still apply a structure: compare unit price and normalize against documentation completeness, receiving ease, and the probability and impact of nonconformance events.
From an industry viewpoint, supplier evaluation for Drf Crefito (and for any Crefito-related supply category) should focus on reliability and risk reduction. When teams compare suppliers, they usually assess the supplier’s ability to deliver not just product, but also the conditions and records that enable safe use and audit readiness.
At a practical level, supplier selection often concentrates on the following areas:
Experts also look beyond these basics and assess maturity of the supplier’s operations. For example:
In many organizations, supplier evaluation becomes a cycle: start with documentation review, then receiving trial shipments, then a periodic performance review. This is especially important for items that have audit-critical requirements.
Procurement is only the beginning. For clinical teams, the question becomes: how does Drf Crefito get used safely and consistently after it arrives?
In many organizations, the integration steps include a sequence that mirrors quality systems principles: verify → store appropriately → track → train → respond to issues.
In that framework, organizations often implement these steps:
This approach helps prevent common operational failures—particularly those caused by mismatched identifiers, missing paperwork, or unclear handling rules. In healthcare environments, these failures are not only “annoying.” They can become compliance issues and patient safety risks.
A practical way to think about integration is to map each step to a “failure mode” and a mitigation. For example:
As organizations mature, they also build feedback loops from the field: staff report issues with usability, documentation clarity, or labeling readability, and quality teams use that feedback to refine acceptance criteria and training.
When buyers discuss Crefito categories, performance may be described in ways that sound absolute. In healthcare supply evaluation, claims are only as good as the evidence behind them. As a discipline, healthcare supply evaluation should rely on verifiable sources such as:
For broader procurement and quality principles, organizations commonly refer to established standards and frameworks. Two widely referenced examples include the World Health Organization (WHO) guidance on medical product quality and safety, and ISO quality management concepts adopted across regulated industries.
Since your prompt does not specify a country/region, the most useful approach is to treat these references as guiding principles rather than as a substitute for local regulatory requirements. If you tell me your country/region, I can align the framework to local expectations and typical documentation patterns you will encounter.
It is also important to clarify what “performance” means in supply contexts. Performance is not only clinical outcomes (which depend on how the product is used) or durability (which depends on handling and storage). In procurement evaluation, performance can also include:
These “operational performance” metrics are often more predictive of day-to-day success than marketing claims. They also tend to be auditable: you can track receiving errors, nonconformance rates, and resolution times.
Below is a practical comparison matrix you can use during supplier conversations. It is framed around objective requirements that procurement and clinical operations teams typically require for healthcare-relevant supplies. You can use it in meetings, in RFQ/RFP responses, and in internal justification documents.
| Evaluation area | What “good readiness” looks like | Why it matters for Drf Crefito / Crefito workflows |
|---|---|---|
| Intended use alignment | Clear documentation stating use-case and constraints | Prevents mismatch between what the product is for and how teams apply it |
| Traceability support | Batch/lot identifiers and reliable record retrieval | Enables investigation if an issue arises and supports audit readiness |
| Labeling and IFU completeness | Correct labeling, readable identifiers, and instructions for handling | Reduces usability errors and improves consistency across staff |
| Quality management documentation | Evidence of quality systems and controlled processes | Lower risk of nonconformance and better supplier accountability |
| Packaging integrity | Protective packing that preserves identity and condition | Supports safe receiving and reduces the chance of damaged or mis-identified items |
| Logistics and storage requirements | Clear guidance on storage stability and delivery conditions | Helps preserve product usability and prevents avoidable wastage |
| Nonconformance handling | Clear process for returns, replacement, and documentation support | Protects continuity of care and shortens resolution time when issues occur |
To make this operational, here is a simple, repeatable workflow used in many professional environments. The main idea is to prevent “first use” until you complete verification steps that connect the product to your clinical protocol and your quality system.
Start by writing down the exact scenario where Drf Crefito (or its related supply category) would be used. Specify the protocol, responsible department, and any internal constraints (e.g., storage capabilities, workflow timing, and staff training requirements).
In practice, teams often create a one-page “use-case brief” that includes:
This brief becomes the basis for selecting the right variant and for writing internal acceptance criteria.
Ask the supplier for relevant documentation that supports safe use and traceability. Ensure it covers labeling, handling/storage requirements, and any required records for your environment.
In mature processes, documentation collection includes multiple layers:
If the supplier offers electronic documentation, request it in a format that your internal systems can store and retrieve (and ensure consistent naming conventions and version control).
On receiving, match the lot/batch information and labels against the order and documentation. Any mismatch should trigger a hold process and escalation, rather than forcing acceptance.
To make this step efficient, experts define an acceptance rule such as:
Additionally, if your facility uses barcode scanning, ensure that identifiers are scannable and correctly formatted. If scanning fails, plan a fallback verification method (manual confirmation and documentation) rather than skipping verification.
Confirm that your facility can meet the storage and handling needs described in the provided IFU or supplier instructions. If you cannot, you should not proceed until requirements are met.
This validation includes practical checks like:
It is common to underestimate storage feasibility when switching suppliers. A different packaging design can change whether the item fits in storage bins, or whether labels remain readable under your storage practices.
Before routine use, ensure staff understand how the item should be handled and used according to the documentation. This step reduces preventable variation across shifts.
Training often focuses on:
Some organizations also run small pilot workflows. A pilot allows staff to encounter real-world issues (e.g., packaging removal steps, label readability under lighting conditions, or how staff access documentation) and resolve them before broad rollout.
Implement a feedback loop: document receiving conditions, any issues, and performance observations. If anything unusual occurs, treat it as a quality signal and investigate promptly.
Feedback tracking can include:
This step is where procurement and clinical operations connect. Procurement can refine supplier evaluation criteria based on real-world receiving outcomes, while clinical teams refine the workflow based on practical use challenges.
Professional due diligence includes knowing when to stop. Consider pausing selection or use when:
To expand this into an operational decision approach, teams typically define “stop criteria” (hard stops) and “monitor criteria” (soft stops). Hard stops might include situations where you cannot ensure traceability or safe handling. Soft stops might include minor documentation formatting issues that can be corrected quickly without affecting safety.
Examples of hard-stop conditions:
Examples of monitor conditions (which still require attention):
Pausing is not a sign of failure; it is a safeguard. In regulated healthcare environments, the goal is to prevent downstream complications that are harder and more expensive to resolve after product enters routine use.
Drf Crefito is a term used in procurement and practice-oriented discussions around a specific healthcare-relevant item or category. In professional use, the very reliable way to understand it is to examine its intended use, documentation, identifiers, and handling requirements as provided by the authorized supplier/manufacturer.
Because the term by itself is ambiguous without additional context, teams typically treat it as a label that must be mapped to a concrete product specification and documentation set before approval.
Compare using a requirements-first approach: documentation completeness, traceability support, IFU clarity, storage/handling feasibility, packaging integrity, and supplier responsiveness for nonconformance. Price matters, but it should be evaluated together with total operational risk and compliance readiness.
To operationalize “requirements-first,” many teams score suppliers against a rubric. A rubric might weight traceability and labeling readiness more heavily than unit price because those factors directly affect patient safety and auditability.
No universal standard price can be stated responsibly without specific product specifications, region, and supplier quotes. Healthcare procurement pricing varies by configuration, regulatory status, logistics costs, and documentation scope. Use quotes and compare them line-by-line.
Also, when quotes differ, ask clarifying questions about what is included: packaging level, documentation bundles, delivery conditions, and return terms. That is where “apples-to-apples” comparisons become possible.
Typically, essential documents include purchase/order records, traceability details (batch/lot where applicable), labeling/IFU information, and any quality-related documentation expected in your regulated setting. The exact requirements depend on your country and the product category classification.
In many healthcare systems, audit readiness also depends on internal records: receiving logs, quarantine/release documentation, training records, and nonconformance logs. Even if the supplier provides external documentation, your internal documentation trail often determines whether the audit is smooth.
Use a hold-and-escalate process: stop acceptance, document the discrepancy, notify the supplier, and ensure your quality and compliance team initiates an investigation. Avoid using items that cannot be matched to identifiers or IFU requirements.
Practical steps include taking photos of labels/packaging if permitted, recording the receiving time and staff involved, logging the order number, and preserving the questionable items in quarantine so they can be inspected or returned.
Yes—mainly operational and compliance risks such as mislabeled items, unclear handling requirements, missing traceability, and inconsistent packaging. These can increase the likelihood of errors and complicate investigations if issues occur.
Even if a product is safe in theory, operational problems can still produce unsafe outcomes—like incorrect handling or failure to ensure correct batch traceability.
Common sources include guidance from international health authorities such as the World Health Organization (WHO), and quality management frameworks like ISO standards used across regulated industries. Your local regulator’s website and published healthcare procurement guidance are also critical.
When applying such guidance, teams should connect general principles to the specific requirements of the product category and local regulatory classification.
In practical terms, Drf Crefito should be approached as a clinical supply topic where the “right” decision depends on verifiable information: intended use, labeling, traceability, and handling requirements. Crefito-related sourcing discussions become very meaningful when teams build a structured comparison and follow a step-by-step vetting workflow before routine use.
Because procurement is accountable not only for purchasing but also for enabling safe clinical operations, the most effective approach is to ensure every Drf Crefito-related choice is supported by a clear paper trail and a realistic workflow integration plan. That includes supplier readiness, receiving acceptance criteria, staff training, storage feasibility, and incident handling readiness.
If you provide the specific product category, your region (or whether you mean a particular market or healthcare system), and any supplier quote structure you’re using, the comparison can be tailored more precisely—without inventing pricing or unverified claims. In procurement work, specificity is what converts generic guidance into actionable decision support.
Note on sourcing and evidence: This article avoids unverifiable pricing and does not claim performance metrics without proper documentation. For general quality and safety principles in medical product handling, teams often reference guidance from recognized health authorities such as WHO and quality frameworks consistent with ISO-style quality management practices.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans
Finding an optimal mix of insurance premiums and direct medical costs is crucial for effective healthcare budgeting. This discussion will delve into tactics to achieve a balance that aligns with your finances.
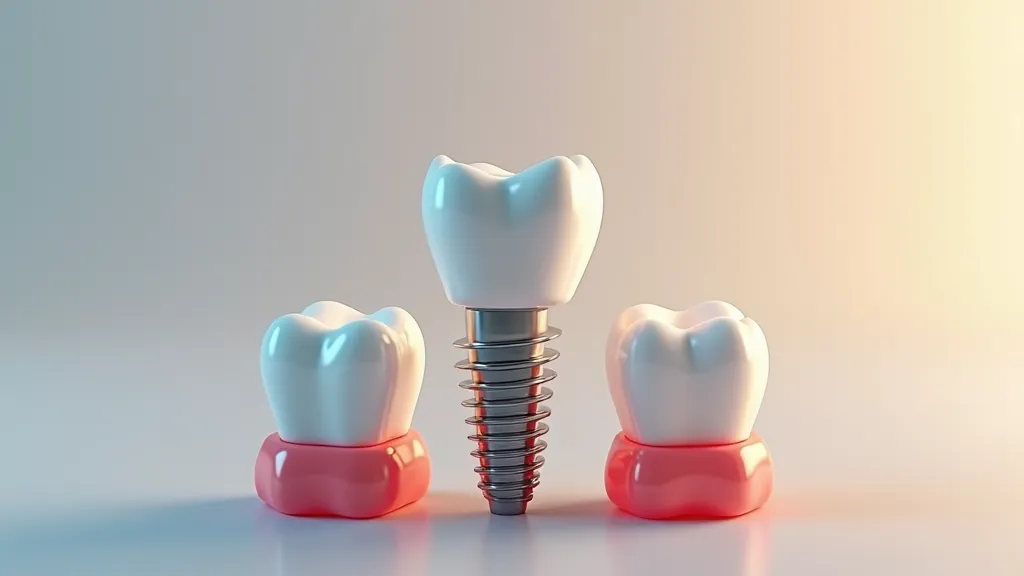
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!
Selecting an adept dentist is critical for ensuring the efficacy and your satisfaction during a dental implant procedure. This in-depth guide is designed to assist you in finding a dental expert who meets your personal requirements, guaranteeing that your path to dental implant success is seamless and fruitful.
Protect Your Perfect Smile: Master the Art of Defending Your Teeth Against Acid Attacks
Though they may tantalize the palate and invigorate the senses, foods and drinks with high acid content are a double-edged sword with regard to oral wellness. Continual exposure to these substances progressively strips away the protective enamel from our teeth, which can lead to increased sensitivity, changes in coloration, and a variety of other dental complications. This composition offers insight into relishing these zesty favorites while safeguarding your teeth from damage.

Discovering Heartis Eagle Mountain
Heartis Eagle Mountain is a prominent senior living community that offers a range of services and amenities aimed at enhancing the quality of life for its residents. Situated in a peaceful setting, it combines exceptional care with engaging activities, providing a holistic environment that caters to seniors' physical, emotional, and social needs.

Unveiling the Top Dental Implant Options for Seniors: Transform Your Smile with the Ultimate Guide to Restored Radiance
The significance of oral health cannot be understated for the elderly population as they are commonly afflicted with tooth loss due to a multitude of factors, including decay and gum disease. Dental implants have risen to prominence as a prime method of teeth replacement, acclaimed for their long-lasting nature, functional prowess, and striking similarity to our own teeth. This discussion delves deeply into the realm of dental implants to demonstrate why they are considered the optimal choice for aged individuals aiming to enhance their smiles and overall life quality.

Boost Your Defenses: 20 Proven Strategies for a Stronger Immune System
Having a robust immune system is essential to protect our bodies from harmful microorganisms and preserve our general health. Although some elements that affect our immunity are out of our hands, many lifestyle decisions can help us enhance our immune defenses naturally. This piece delves into 20 practical methods to empower your immune system, increasing your capacity to ward off diseases and sicknesses.
