Pmoc Abrava is a treatment-related material often discussed in dental workflows for its role in achieving stable, repeatable clinical outcomes. This guide explains what “Pmoc Abrava” commonly refers to in professional conversations, how clinicians evaluate it, and what buyers should consider when comparing supply options, quality controls, and practical fit in day-to-day practice.
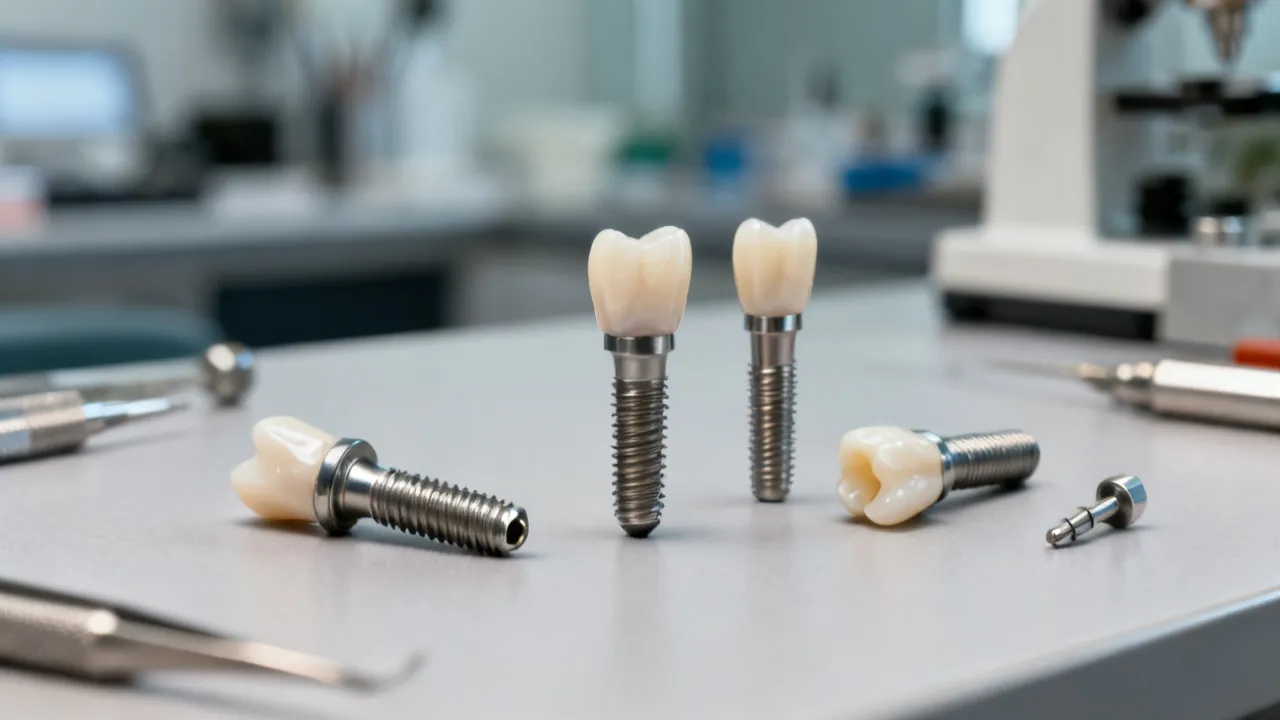
In day-to-day dental practice, “Pmoc Abrava” is frequently mentioned when clinicians and purchasing teams discuss performance consistency across procedural steps. While the exact meaning can vary by supplier catalog and regional terminology, the core reason professionals compare Pmoc Abrava options is practical: they want predictable handling characteristics, dependable manufacturing standards, and reliable documentation that supports clinical decision-making.
For clinicians, the comparison often starts at the point where the product meets reality—right at the chairside workflow. For procurement teams, the comparison starts where risk and accountability live—traceability, labeling, regulatory readiness, and the ability to prove exactly what was used and when. When a practice compares “Pmoc Abrava” choices, they are essentially comparing how each option behaves inside a controlled process rather than merely evaluating a material in isolation.
From an industry perspective, evaluating Pmoc Abrava is less about chasing a single “miracle” attribute and more about assessing how the material integrates with the surrounding protocol—case selection, handling time, compatibility with adjacent components, sterility or quality assurance practices, and traceability. For practices planning upgrades or onboarding new suppliers, the comparison process matters as much as the product itself.
It’s also worth noting that in regulated healthcare environments, the way a product is documented is not “bureaucracy for bureaucracy’s sake.” Documentation is what allows a clinic to remain consistent across time, staff changes, inspections, and adverse event investigations. Even when two products appear similar on a shelf, the one with stronger documentation, clearer IFU alignment, and more consistent batch-to-batch behavior is usually the one that best supports patient safety and operational stability.
In practice, these items function like a checklist that connects clinical technique to procurement responsibility. A clinic that focuses only on handling may underestimate documentation gaps; a clinic that focuses only on documentation may miss real-world workflow friction. Professionals compare Pmoc Abrava options because they want both dimensions to align.
Because “Pmoc Abrava” can appear as a shorthand used across different catalogs or vendor families, objective interpretation requires context. In very procurement and clinical conversations, the phrase points to a product within a broader dental system rather than a standalone “one-size-fits-all” solution. Professionals typically use the term to reference:
Instead of relying on marketing language, clinicians generally confirm intended use by checking the supplier’s labeling and instructions for use (IFU), plus any applicable regulatory documentation for the market where the product will be used.
Another reason professionals pay close attention to wording is that supplier catalogs sometimes use internal naming conventions that may be loosely similar across product lines. Two vendors might both mention a term resembling “Pmoc Abrava,” but they might refer to different compositions, different packaging formats, different intended uses, or different regulatory categories. That is why professional comparisons always begin with exact identification, not with assumptions based on a shared label.
Industry experts often stress that outcomes are rarely determined by one item alone. In dental workflows—especially those involving multiple materials, sequential steps, and specific handling timelines—each element must cooperate with the rest. When practices compare Pmoc Abrava options, the main question becomes: “Does this option behave consistently with our protocol?”
For example, procurement teams look at whether the product’s handling aligns with chairside efficiency, whether the clinic can store it properly without degrading performance, and whether documentation supports audit readiness. Clinicians look at application predictability, whether the product behaves as expected during mixing or placement (if applicable), and whether adjacent steps remain stable over time under normal practice conditions.
To make this concrete, consider a common scenario in many clinics: a material is used during a step that depends on timing—such as a procedure where moisture control, curing windows, or set-time constraints determine success. If the chosen Pmoc Abrava option has different working time characteristics from what staff are accustomed to, it may lead to rushed steps, increased remakes, or subtle inconsistencies. These process-level deviations can be more consequential than small differences in material performance claims.
In addition, dental clinics frequently experience variations in patient flow: appointment timing differs, staff availability changes, and clinical settings may not always match controlled laboratory conditions. A workflow lens comparison helps ensure that the product remains reliable when the clinic environment is not perfectly controlled—because in real practice, it never is.
You may encounter wide variation in listed prices for materials and kits grouped under names like Pmoc Abrava. However, objective value analysis goes beyond unit cost. The very defensible approach is to estimate total cost per usable clinical outcome, factoring in:
When teams compare price, they should ask suppliers for documentation (not just quotes). Even when price seems lower, missing IFU details, unclear traceability, or limited technical support can increase overall risk—and risk has a cost.
Value is also connected to continuity of supply. A “cheap” option that requires frequent reorder due to minimum order quantities, long lead times, or fragile storage constraints can create operational bottlenecks. If a clinic runs out mid-week, staff may improvise with substitutes, and the workflow stability that professionals are trying to achieve will be undermined. Therefore, pricing comparisons should include lead time, availability history, and the supplier’s ability to deliver consistent packaging and labeling across shipments.
Another dimension of cost is rework. If one option leads to higher discard rates, more remake attempts, or more time required for chairside steps, the clinic’s labor costs and patient experience are affected. Professionals comparing Pmoc Abrava options often quantify this by tracking time-to-completion, number of remakes, and the frequency of wasted or discarded materials over a pilot period.
Procurement professionals typically separate “a supplier who sells” from “a supplier who supports quality.” For Pmoc Abrava items, objective supplier due diligence usually includes:
In the absence of verifiable supplier documentation, even a seemingly competitive price can be misleading. Professional standards prioritize repeatability, patient safety, and auditability.
Supplier support is not just about answering questions—it’s also about ensuring the clinic has the right information at the right time. For example, if a clinic notices unexpected behavior during use, a responsive technical team can help determine whether the issue relates to handling steps, storage conditions, batch-specific manufacturing issues, or user technique. Without that support, clinics may waste time guessing, which can increase risk and cost.
Additionally, some suppliers provide training materials, application guides, or compatibility notes with commonly used dental systems. Even when these resources are not required, they often reduce onboarding time. For a practice that is standardizing across multiple operatories or multiple branches, training consistency becomes a key operational advantage.
If you are planning procurement in a region with high patient volume or specific regulatory expectations, local clinic workflow matters. For instance, in many countries, practices often prioritize documentation readiness for inspections and may require specific storage practices for regulated materials. While branding and purchasing channels vary, the evaluation criteria—traceability, IFU clarity, and compatibility—remain consistent. Clinics near major business districts or teaching hospitals often emphasize standard operating procedures (SOPs) and staff training consistency, which can influence which Pmoc Abrava option proves easiest to adopt.
To keep decisions grounded, consider running a controlled internal trial. Use the clinic’s standard protocol, record handling observations, and document any deviation or learning curve friction. This “real-world fit” test typically reveals more than spec sheets alone.
Localization also affects how clinics handle procurement administrative tasks. Different markets may have differing expectations for record retention, labeling requirements, and batch identification practices. Even if your team is experienced, shifting to a new supplier can introduce subtle administrative changes. Comparing Pmoc Abrava options should therefore include not only the clinical material behavior but also whether the paperwork, labels, and traceability information are practical to use in your local documentation system.
For example, if your clinic uses an electronic inventory system that relies on specific barcode formats or lot-number import structures, you’ll want to confirm that the supplier’s packaging supports that workflow. Otherwise, staff may spend time manually entering identifiers, increasing the risk of errors during audits or recalls.
Below is a practical comparison table designed to support objective selection. It focuses on verification points rather than promises. Replace placeholders with the details from your specific supplier quotations and IFUs.
| Evaluation category | What to ask/verify | Why it matters |
|---|---|---|
| Product identification | Exact catalog name, component type, intended use, and labeling references | Ensures “Pmoc Abrava” corresponds to the same clinical function across options |
| Regulatory status | Applicable regulatory category and market-specific documentation | Supports safe compliance and audit readiness |
| Traceability | Lot/batch numbers, documentation provided with each shipment | Enables recalls and quality review if issues arise |
| Instructions for use | IFU availability and clarity on storage, handling, and sequencing | Reduces procedural variability and misuse risk |
| Compatibility | Compatibility notes with your existing dental system materials/equipment | Prevents failures caused by mismatched workflow steps |
| Quality controls | Documented quality checks and acceptance criteria | Improves consistency across batches |
| Supplier support | Training resources, technical contact, escalation process | Shortens onboarding time and reduces operational uncertainty |
| Commercial terms | Pricing structure, minimum order, lead time, returns policy, and expiry handling | Prevents budget surprises and prevents expired stock accumulation |
Because product naming can be inconsistent across markets, many clinics anchor decisions to established regulatory and safety frameworks. For example, clinicians typically rely on general principles from:
For background reading, relevant frameworks include the EU Medical Device Regulation (MDR) and comparable national requirements; clinics and procurement teams also consult official guidance from their local competent authorities and rely on the manufacturer’s IFU as the closest-to-use instructions.
In addition to formal regulatory guidance, many practices use internal QA frameworks that mirror the spirit of these regulations: consistent documentation, controlled adoption processes, and defined responsibilities for storage, usage, and inventory management. Comparing Pmoc Abrava options is more successful when clinics align their internal processes with these baseline quality expectations.
For example, an internal QA-oriented comparison may include verifying that staff members understand the IFU’s sequence steps, ensuring that storage conditions are monitorable (e.g., documented temperature ranges where applicable), and confirming that batch numbers can be recorded easily in patient records. These tasks might feel “admin,” but they are exactly what prevent procedural drift over time.
A common reason clinics struggle when adopting new materials is that a “pilot” is treated like an informal trial instead of a structured evaluation. A stronger pilot for Pmoc Abrava typically includes clear success criteria and structured observation points.
For example, you can define what “success” means in both clinical and operational terms:
During the pilot, encourage staff to document “near-misses,” not only outcomes. Near-misses include moments when the team nearly deviated from the IFU, ran into uncertainty about handling, or experienced confusion due to packaging or labeling. Those events are valuable because they point to where the workflow needs support—training materials, SOP wording, or supplier documentation updates.
“Do not skip” requirements also include internal escalation processes. If something unexpected occurs—unusual behavior, handling failures, or any suspected quality issue—staff should know exactly who to contact, what details to capture, and how to preserve evidence (e.g., retaining packaging with lot numbers). This is particularly important for audit readiness and for quality investigations that may follow adverse events.
In my experience reviewing procurement and onboarding practices across dental specialties, the clinics that adopt “Pmoc Abrava” options very successfully tend to:
Conversely, adoption tends to struggle when product terminology is unclear, documentation is incomplete, or the clinic expects one product name to guarantee performance without protocol alignment.
Another factor that frequently determines success is inventory and storage design. Clinics that manage stock systematically—labeling shelves correctly, storing products according to IFU, and using first-expiry-first-out practices where applicable—tend to report fewer incidents of degraded performance. When storage discipline is weak, the clinic may wrongly attribute handling inconsistencies to the product’s intrinsic properties rather than to storage drift.
When professionals compare Pmoc Abrava options, they often expand the evaluation beyond the product itself. The core question is: “How does the choice change our day-to-day workflow?”
Consider these practical workflow-impact dimensions:
These factors directly affect appointment flow and staff satisfaction. In high-volume settings, workflow friction can be the difference between a smooth adoption and a prolonged period of frustration that ultimately results in either reverting to the previous option or changing the protocol again.
Traceability may feel like a procurement concern, but it is also a clinical safety tool. If a patient experiences an issue that triggers investigation—whether due to material quality, procedural deviation, or storage conditions—traceability helps answer “what was used” quickly and accurately. When comparing Pmoc Abrava options, clinics should ensure that traceability is not only possible but also practical.
Practically, this means verifying:
Clinics that build a clear documentation path during adoption often experience smoother audits and fewer delays in quality investigations. Even if an adverse event never occurs, having traceability in place reduces uncertainty during stressful moments.
Compatibility is one of the most common “hidden variables” when professionals compare Pmoc Abrava options. Two products may both be approved for a general category of use, but they can still differ in how they interact with adjacent steps.
Compatibility checks can include:
In a pilot, compatibility becomes visible. Staff may observe that the product works well in one operator’s hands but not another’s, or that it behaves differently depending on how earlier steps were performed. Those observations are valuable—they help determine whether training updates are needed or whether the product selection should change.
Even if Pmoc Abrava options have similar performance claims on paper, staff behavior can introduce variation. Professionals therefore evaluate supplier support and training readiness as part of total value.
Training should address more than “how to open the packaging.” It should cover:
Supplier training can be especially valuable for practices standardizing across multiple operatories. When onboarding is inconsistent, different staff members may interpret the IFU differently, leading to procedural drift. That drift can produce outcomes that appear “material dependent” when the true cause is operator variation.
Therefore, when comparing Pmoc Abrava options, procurement and clinical leaders should align on who needs training, what competency checks will be performed, and how the clinic will evaluate whether training was effective.
Another practical reason professionals compare Pmoc Abrava options is supply continuity. A product that is hard to reorder, subject to long lead times, or prone to packaging changes can create operational risk.
Expiry management is closely tied to continuity. Clinics that cannot reliably predict usage rates may accumulate stock that expires, increasing waste and cost. When comparing suppliers, teams should consider:
Expiry risk can also distort clinical evaluation. If a pilot uses product with different remaining shelf-life across batches, staff may observe performance changes and attribute them to the supplier rather than to expiry or storage drift. To reduce this risk, pilot design should standardize batch shelf-life as much as reasonably possible.
Commercial terms can influence whether Pmoc Abrava adoption is smooth or disruptive. Professionals compare not only the purchase price but also the broader purchasing contract elements that affect risk handling.
Relevant contract terms to evaluate include:
These elements matter because they determine how quickly a clinic can correct problems if they arise. In fast-paced dental operations, delays in replacements or documentation can create appointment disruptions.
Even with strong selection processes, no clinic can guarantee that every batch will behave exactly as expected. When performance issues are observed, the appropriate response is structured and evidence-based.
If your clinic notices a performance issue with a Pmoc Abrava option, professionals typically recommend these steps:
This approach ensures that the clinic does not guess and does not normalize problems. It also ensures that the supplier can investigate with accurate information, potentially preventing broader issues.
Q1: What exactly does “Pmoc Abrava” refer to?
A: In practice, “Pmoc Abrava” typically denotes a specific dental material or kit component referenced by supplier terminology. Because naming can differ by catalog and region, the objective approach is to match the term to the supplier’s labeling and the corresponding instructions for use (IFU).
Q2: How should I compare Pmoc Abrava options when prices differ?
A: Compare total value, not only unit price. Evaluate usability/yield, waste risk, expiry/stock handling, traceability documentation, IFU clarity, and supplier technical support. A slightly higher price can be cheaper overall if it reduces waste and onboarding time.
Q3: Are there special storage or handling requirements?
A: Storage and handling must follow the IFU provided by the manufacturer. Clinics should not assume requirements based on similar-sounding products. Verify storage conditions, shelf-life constraints, and any specific handling precautions with the documented IFU.
Q4: What supplier information should I request before ordering?
A: Request product identification details, market-specific regulatory documentation (where applicable), lot/batch traceability approach, IFU availability, quality documentation appropriate to the product category, and the supplier’s technical support contact process.
Q5: Can I test Pmoc Abrava in my clinic before purchasing large quantities?
A: Yes, many clinics run a limited pilot. The top practice is to confirm the product’s intended use and eligibility criteria, document handling observations, and review both process stability and clinical outcomes using your standard protocol.
Q6: If I notice a performance issue, what steps should I take?
A: Stop using the product for new cases, document what you observed (batch/lot, conditions, timeline), and consult the manufacturer’s technical support and applicable regulatory reporting pathways. Avoid guessing the root cause without evidence.
Q7: Does this guide include location-specific procurement advice?
A: The evaluation framework is designed to be location-agnostic in order to remain objective. However, clinics should adapt to local regulatory expectations, inspection routines, and documentation requirements. Replace supplier and market details with your own IFU and compliant purchasing documentation.
“Pmoc Abrava” is best understood not as a vague brand promise, but as a product reference that must be validated through labeling, IFU instructions, traceability records, and compatibility with your clinic’s existing workflow. A disciplined comparison approach—covering product identification, quality evidence, handling fit, workflow impact, supplier support, and total value—helps procurement and clinical teams make decisions that are both operationally efficient and responsibly grounded in documented requirements.
When clinics treat adoption as a process—structured pilots, verified documentation, standardized SOPs, and evidence-based escalation—they reduce avoidable risk and improve consistency across operators and time. In that sense, professionals compare Pmoc Abrava options not because they chase marketing claims, but because they prioritize predictable, auditable performance within the realities of daily dental practice.
Note on data integrity: This article avoids unverified claims and focuses on verification steps and professional evaluation practices. For any product-specific claims (performance, regulatory status, handling), always consult the manufacturer’s IFU and official regulatory documentation for your market.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans
Finding an optimal mix of insurance premiums and direct medical costs is crucial for effective healthcare budgeting. This discussion will delve into tactics to achieve a balance that aligns with your finances.
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!
Selecting an adept dentist is critical for ensuring the efficacy and your satisfaction during a dental implant procedure. This in-depth guide is designed to assist you in finding a dental expert who meets your personal requirements, guaranteeing that your path to dental implant success is seamless and fruitful.
Protect Your Perfect Smile: Master the Art of Defending Your Teeth Against Acid Attacks
Though they may tantalize the palate and invigorate the senses, foods and drinks with high acid content are a double-edged sword with regard to oral wellness. Continual exposure to these substances progressively strips away the protective enamel from our teeth, which can lead to increased sensitivity, changes in coloration, and a variety of other dental complications. This composition offers insight into relishing these zesty favorites while safeguarding your teeth from damage.

Discovering Heartis Eagle Mountain
Heartis Eagle Mountain is a prominent senior living community that offers a range of services and amenities aimed at enhancing the quality of life for its residents. Situated in a peaceful setting, it combines exceptional care with engaging activities, providing a holistic environment that caters to seniors' physical, emotional, and social needs.

Unveiling the Top Dental Implant Options for Seniors: Transform Your Smile with the Ultimate Guide to Restored Radiance
The significance of oral health cannot be understated for the elderly population as they are commonly afflicted with tooth loss due to a multitude of factors, including decay and gum disease. Dental implants have risen to prominence as a prime method of teeth replacement, acclaimed for their long-lasting nature, functional prowess, and striking similarity to our own teeth. This discussion delves deeply into the realm of dental implants to demonstrate why they are considered the optimal choice for aged individuals aiming to enhance their smiles and overall life quality.

Boost Your Defenses: 20 Proven Strategies for a Stronger Immune System
Having a robust immune system is essential to protect our bodies from harmful microorganisms and preserve our general health. Although some elements that affect our immunity are out of our hands, many lifestyle decisions can help us enhance our immune defenses naturally. This piece delves into 20 practical methods to empower your immune system, increasing your capacity to ward off diseases and sicknesses.
