This guide explains how “Mismile Sheffield” relates to planning for affordable dental implants, reviewing reputable care pathways across English-speaking and other major language communities. It covers what low-cost implant marketing typically includes, how to assess treatment plans, estimated implant-only cost ranges by country, and practical steps to reduce total expenses—without compromising clinical standards.
If you are exploring Mismile Sheffield as a starting point, the very important takeaway is not the branding itself—it’s the process you should follow. Dental implant “affordability” varies widely based on clinical complexity, surgeon experience, implant system selection, restoration type, and local business models. A professional approach means verifying the treatment plan, confirming what is included in quoted prices, and understanding the typical trade-offs clinics make when advertising low-cost dental implants.
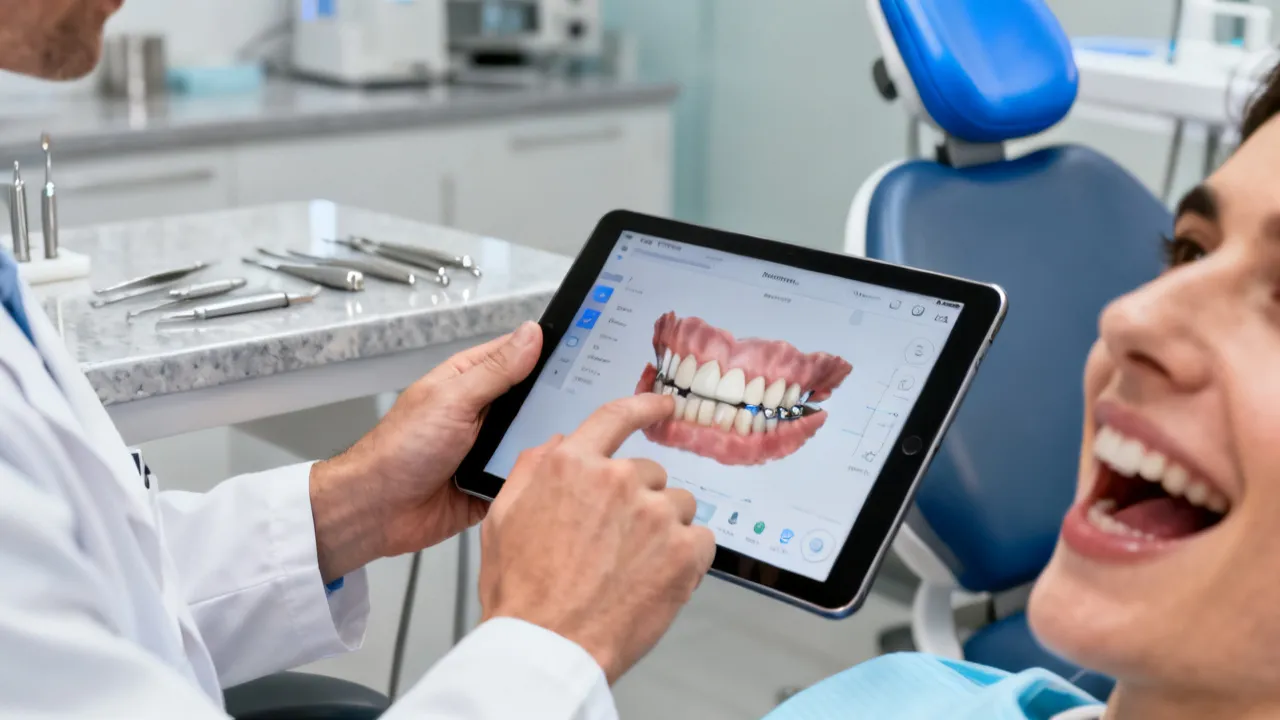
From an expert perspective, the smart way to use any local or brand-associated entry point (such as Mismile Sheffield) is to translate marketing claims into concrete clinical questions: the number of implants, whether bone grafting is required, the type of abutment and crown material, expected timelines, and which diagnostic tools are used for planning. When those variables are clarified, you can compare options fairly—even across different countries and languages.
In other words, the “Mismile Sheffield” search intent often signals a patient who is actively trying to solve a real problem—missing teeth, chewing limitations, speech issues, aesthetics concerns, and the financial pressure that can accompany dental care. Those practical realities should drive your plan. But affordability should never be treated as a single line item; it should be evaluated as a full pathway that includes diagnosis, implant placement, healing and follow-up, restoration fabrication and placement, and ongoing maintenance. The cheapest-looking quote can become expensive if it omits critical components (imaging, grafting, abutments, temporaries, screw-retained vs cement-retained design, precision fit processes, or guaranteed follow-up).
To turn this into actionable planning, you should approach any implant quote the way you would approach a “total cost of ownership” for a long-term investment. Ask: what is the expected lifespan of the restoration? What maintenance is planned and what happens if something fails (chipped crown, peri-implant inflammation, screw loosening, veneer fracture, a need for redesign)? Do they provide a documented warranty or service plan? Are the materials and components clearly identified? Are they using modern planning methods that reduce risk, such as CBCT imaging or digital workflows for precise implant positioning? These questions are particularly important when you’re comparing “low-cost” options, because marketing language can sometimes compress multiple phases of care into a single low headline price.
Finally, treat your own eligibility as part of the “affordable” equation. If your mouth requires additional work—periodontal therapy, infection control, sinus considerations, ridge augmentation, orthodontic spacing, or changes to bite alignment—the true “affordable” path might involve staged treatment that starts with stabilization before implants. Clinics that frame low cost without discussing these prerequisites are often under-specifying the scope. A responsible clinic will connect cost to clarity: they will say what you need now, what you might need later, and which decisions depend on exam and imaging findings.
Dental implants are widely recognized as a high-quality good tooth replacement option. However, implant treatment can be expensive because it blends multiple steps: diagnostics (often CBCT/3D imaging), surgical placement, healing, and prosthetic restoration (crown/bridge). In many markets, the overall expense is driven by clinical overhead, materials, and the professional workflow required for predictable outcomes.
That is why patients increasingly search for “low-cost dental implants.” In practice, low-cost positioning may come from one or more of the following:
From a clinical safety standpoint, the key issue is not whether a price is “low,” but whether it reflects the full scope needed for success in your specific mouth. Two patients with different bone levels, bite forces, infection control needs, and aesthetic requirements can receive very different treatment components, even if the word “implant” appears in the quote.
It also helps to understand that international discussions often include differences in healthcare financing, regulation, and supply chain economics. For example, the total cost of implants can vary due to:
Low-cost advertising can be influenced by these factors, and that’s why you need to “normalize” comparisons. A quote isn’t just a number—it’s a statement about what is included, what is excluded, and what assumptions the clinic made about your clinical scenario.
In addition, “low-cost” may mean different things to different patients. For someone missing a single molar, affordability may mean a limited procedure with a simple crown. For someone with multiple missing teeth and bone loss, affordability might mean accepting a different restoration type (for example, overdentures supported by implants rather than multiple individual crowns). For someone with high aesthetic demands, affordability might still require higher-spec prosthetic materials or precise screw access and gingival management—because aesthetics isn’t optional, even when the budget is.
Before you request quotes, it helps to check how major dental information platforms describe the “low-cost” concept. Some focus on implant procedures, others on insurance guidance or dental tourism. Below is a comparison table of websites that commonly provide educational information on affordable implant pathways.
When reviewing educational sources, you should notice whether the site provides:
Some pages may be heavily promotional, while others may offer more neutral educational guidance. Both can be useful, but your evaluation should always return to clinical and financial transparency.
| Website (information focus) | Common emphasis |
|---|---|
| dentalviews.com/low-cost-dental-implants | Educational content on benefits of implants and cost-related considerations |
| atlanticdentalgrp.com | Clinic-service overview (cleanings, orthodontics, implants, and practical appointment access) |
| dentavacation.com | Dental tourism approach, including cost comparisons and travel-oriented guidance |
| rockvilledentalarts.com (ADHP-related page) | Insurance-planning guidance and how coverage can reduce expenses |
source: [www.dentalviews.com](https://dentalviews.com/low-cost-dental-implants/) • [www.atlanticdentalgrp.com](https://www.atlanticdentalgrp.com/) • [www.dentavacation.com](https://www.dentavacation.com/) • [www.rockvilledentalarts.com](https://rockvilledentalarts.com/es/)
To make these sources more useful to your personal planning, convert the information into a question list you can bring to your consult. For example, if a site discusses the role of imaging, ask the clinic: “Will you generate a surgical plan based on CBCT, and can you show me where the implant will be placed relative to nerves, sinuses, and other anatomical landmarks?” If a site discusses insurance planning, ask: “What documentation do you provide so my insurer can review medical necessity, and does the clinic offer itemized codes or detailed summaries?” If a site focuses on dental tourism, ask: “How is the follow-up handled if complications occur after I return home?”
In short, use educational and informational pages to sharpen questions—but use in-person (or properly conducted remote) clinical evaluation to make the final decision.
Low cost is rarely a single trick; it’s usually a combination of preparation, documentation, and smart negotiation of the treatment package. Below is a detailed, step-by-step guide you can apply when planning implants in English-speaking and other major language communities (including Spanish and Portuguese-speaking countries). The same clinical logic applies regardless of language: you want the right diagnosis, a realistic implant plan, and a restoration that matches your functional and aesthetic needs.
For many patients, “affordable implant planning” is not just about paying less for the same procedure—it’s also about selecting the right treatment pathway that offers the best value given their anatomy and goals. Value can mean fewer surgeries, fewer appointments, and simpler restoration designs where clinically appropriate. It can also mean choosing staged treatment and addressing risk factors first to reduce the chance of failure and costly rework later.
When you receive an estimate, request a breakdown that clarifies:
Additionally, ask for the scope to separate at least these components:
Low-cost plans that do not provide itemization create risk because you might later discover that what you thought was included is billed separately. For example, a quote may include implants and basic surgery, but exclude:
Your goal is to eliminate uncertainty. Ask for clarity in writing.
In many affordable-care journeys, clinics may rely more on standard assessment models; however, implant placement benefits from 3D planning in complex cases. Ask whether they use CBCT or equivalent imaging and how it informs placement and safety margins.
Even if you’re trying to reduce cost, remember that imaging is not merely an “extra expense”—it is often the information that prevents catastrophic mistakes. If a clinic uses older or more limited imaging in a case where 3D planning is recommended, the risk of improper angulation, insufficient safety distances from nerves or sinuses, or poor placement relative to prosthetic alignment may increase.
Consider asking:
Imaging matters differently depending on case type. If you’re having implants in the aesthetic zone (front teeth), accurate placement relative to roots, bone contours, and future crown position is especially important. If you’re in the lower molar region, nerve proximity and bone density influence safety. If upper molars are involved, the sinus floor and sinus considerations matter. Clinics that can explain these factors are more likely to deliver predictable results.
To reduce costs responsibly, aim to optimize controllable factors before treatment:
Clinical eligibility is not just “do you have enough bone.” It includes the whole environment around the implant: gums, saliva consistency, inflammation control, oral hygiene ability, bite stability, and whether you can commit to follow-up and maintenance. A cost-focused approach should actually include the costs of preparing the mouth for success. Skipping eligibility steps can result in implant failure, which then becomes far more expensive than a slightly higher initial quote.
Ask the clinic whether they will:
Risk management can also reduce “hidden costs.” Many patients don’t realize that if a clinic doesn’t adequately plan for bite forces, they may later need adjustments or replacement restorations. A properly planned occlusion and prosthetic design is often a cost-saving move over the long term.
A frequent misunderstanding in low-cost dental implant advertisements is that prices may refer to implant surgery alone rather than the full prosthetic restoration. Make sure you compare like with like. If one clinic quotes “implant-only,” ask what the restoration costs separately.
When you request an itemized quote, ask for separate line items and totals for:
To make comparisons fair, ask for a “total treatment cost” for each provider that includes at least one of the following scenarios: the final restoration type they propose, and the expected number of implants. If a clinic proposes a different number of implants than another clinic, discuss why (bone availability, design philosophy, or prosthetic constraints). Some cost differences come from a different restoration strategy, not necessarily lower clinical quality.
Restorations determine much of the final comfort and chewing performance. When comparing offers, ask how the crown or bridge is fabricated, the expected fit process, and what quality checks are performed.
In affordable planning, prosthetic workflow is where many differences appear. “Low-cost” may reduce labor or materials in ways that affect fit and long-term durability. Ask whether the final restoration is made through a digital or conventional workflow, who designs it, and how the fit is verified at placement.
Useful questions include:
Also ask about comfort: will they provide a temporary restoration and adjust it during healing? Will they manage soft tissue aesthetics (emergence profile, gingival contour) if the implant is in an aesthetic area? If you’re concerned about appearance, you should treat prosthetic planning as a major part of the “value” story, not an afterthought.
For people who prefer care in their native language, localized clinic websites can improve communication and consent quality. For example, in Spanish-speaking settings, clinics such as Rockville Dental Arts (with Spanish-language materials) and specialized mini-implant centers like Union City Mini Dental Implants often present information tailored to Spanish-speaking patients. Likewise, Portuguese-speaking communities may find clinic and insurance information through providers such as Rubi Odonto, Odontologia Velasco, and DentalVidas.
However, regardless of language, you should still request the same documentation: imaging approach, implant count and plan, prosthetic materials, and total estimated cost.
Language support matters because informed consent and aftercare instructions can be compromised if translation is poor. After implant surgery, patients must follow medication instructions, manage swelling and hygiene, and attend follow-up visits. If you don’t fully understand the steps, you might miss critical post-op care, increasing risk. Choose a provider who can explain risk and expected outcomes in a way you understand, and request written aftercare instructions in your language.
Dental tourism can reduce expenses, but it changes the follow-up logistics. If you travel for treatment, ask:
Additionally, consider the timing of travel. If you fly in and have multiple staged steps without the possibility of local follow-up, your risk increases. Implants often require healing time before final restoration, and you may need adjustments to temporaries or prosthetic fit. Some programs offer remote coordination, but you should still plan for in-person support if complications occur.
Questions you can ask dental tourism coordinators or clinics include:
Some dental tourism platforms, such as DentaVacation, explain how patients compare costs across countries and arrange travel. Use those resources as starting points for research—not as substitutes for in-person clinical evaluation.
In certain markets, insurance or health plans may reduce out-of-pocket expenses, though coverage for implants differs widely. Insurance education pages can help you understand how to apply and what to request from providers. For example, American Dental Health Plan-related guidance is often discussed in ways intended to help patients understand coverage options and how to use plans strategically.
If insurance is involved, focus on how implant treatment is documented. In some healthcare systems, implants may be considered elective or may require specific clinical criteria to be approved. Ask the provider:
Also, check whether your plan covers the prosthetic stage and lab work. Many patients discover late that a plan covers some diagnostics or certain procedures but not the final crown/abutment components.
If you aim to reduce cost, ask whether the clinic can offer:
Negotiating can be beneficial, but it should be based on clarity and clinical appropriateness. Avoid negotiations that result in vague promises such as “it will be cheaper after we start” or “we’ll see later if you need grafting.” While some clinical decisions are indeed confirmed during surgery, a safe practice is to provide an evidence-based plan for what is likely and what contingency exists.
You can negotiate for predictable value by asking:
Ultimately, negotiations are strongest when both parties agree on a written scope and timeline.
To support budgeting, the table below presents implant-only cost ranges for selected countries based on widely cited reference ranges. These are intended as directional estimates, not personal quotes. Actual prices depend on treatment complexity, surgeon fees, imaging requirements, and whether grafting is needed.
It is important to interpret “implant-only” as a partial component. Many patients see a low implant-only price and assume their total implant treatment will match that number. In reality, the total cost often includes abutments, crowns/bridges, and additional surgical phases or bone augmentation. Therefore, you should treat the table as a starting point for comparisons rather than a reliable budgeting tool.
| Country | Currency | Price range (implant-only) |
|---|---|---|
| United States (US) | USD | $3,000 - $6,000 |
| United Kingdom (GB) | GBP | £2,000 - £2,500 |
| Australia (AU) | AUD | AU$3,500 - AU$6,500 |
| Canada (CA) | CAD | CA$3,000 - CA$5,500 |
| Spain (ES) | EUR | €1,500 - €2,500 |
| Chile (CL) | CLP | CLP$800,000 - CLP$1,500,000 |
| Mexico (MX) | MXN | $15,000 - $25,000 |
| Colombia (CO) | COP | $2,000,000 - $4,000,000 |
| Peru (PE) | PEN | S/ 3,000 - S/ 6,000 |
| Argentina (AR) | ARS | $80,000 - $150,000 |
| Brazil (BR) | BRL | R$3,000 - R$8,000 |
| Portugal (PT) | EUR | €1,000 - €2,000 |
When you use these figures, also factor in other costs that can vary by country and clinic:
A “low” implant-only quote can be misleading if the restoration and augmentation costs are not comparable. For budgeting, you should always ask for a “complete package total” rather than relying on implant-only figures.
Affordable implant journeys are shaped by practical factors—communication comfort, logistics, and understanding of documentation. In multi-language searches, patients often prioritize clinics that can explain steps clearly and support decision-making.
“Language-local context” doesn’t only mean translation. It includes appointment scheduling convenience, the ability to explain post-op instructions, and the clinic’s responsiveness when patients have concerns during healing. These factors affect outcomes and costs indirectly: if a patient can’t communicate pain changes or doesn’t understand hygiene steps, complications may arise that require additional treatment.
In English-speaking markets, patients frequently compare clinical credentials, clinic follow-up policies, and the scope of what is included in a quote. Many also consider insurance structures. For example, dental service pages like those from Atlantic Dental Group typically emphasize appointment access and a broad array of services (cleaning, orthodontics, implants, and emergency dental care), which can be important when planning multi-stage treatment.
In these contexts, patients also often ask for:
Because patients often have access to comparative reviews and online resources, clinics sometimes compete on speed and affordability. Yet the best decision-making still depends on whether the plan matches your anatomy and needs.
In Spanish-speaking communities, Spanish-language clinic materials can reduce friction during consent and aftercare planning. For instance, Rockville Dental Arts provides Spanish-language clinic information and service descriptions, including implants and emergency care. Similarly, specialized mini-implant clinics such as Union City Mini Dental Implants may highlight mini-implant suitability for limited tooth replacement areas—an approach that can sometimes reduce complexity compared with more extensive reconstructions, when clinically appropriate.
Additionally, patient education resources such as those published by international health organizations can help Spanish-speaking readers understand treatment basics. For example, Cigna’s educational materials on dental implants can support general comprehension when comparing provider offers.
When Spanish-speaking patients look for affordable options, an important practical point is aftercare comprehension. Patients should confirm they can understand:
If the clinic can provide written instructions in Spanish and explain them verbally, adherence improves—often reducing the chance of costly complications.
In Portuguese-speaking environments, clinics and dental plan providers often communicate availability, service ranges, and ongoing support. Rubi Odonto (Santo André, São Paulo) and Odontologia Velasco (São Paulo) are examples of clinics that publicly present services such as orthodontics, whitening, and implants, along with emphasis on experienced teams and modern technology. Meanwhile, dental plan providers like DentalVidas may support patients by offering plan options and describing emergency service access—factors that can matter during long healing intervals.
In these contexts, affordability discussions may include the value of “continuity of care.” Patients may ask: who will handle the implant follow-ups and adjustments? Will the clinic remain available during the healing period? Are there included check-ups? Continuity can reduce the need to travel long distances later, which becomes a financial factor even if the implant procedure is cheaper initially.
Even though pricing is central, implant success depends on biology and prosthetics. When a clinic positions itself as “low cost,” the biggest clinical variables to monitor are the same variables you would check at any price point:
As a practical rule: “low cost” becomes risky if it means skipping essential diagnostics, rushing healing, or under-specifying restorations. The safer path is to reduce costs by choosing appropriate case pathways and negotiating transparent packages rather than cutting clinical corners.
To make “low-cost” decision-making safer, consider thinking in terms of three categories: (1) steps that are mandatory for safety, (2) steps that may be optional depending on your case, and (3) steps that are “value add” but not strictly required for everyone. A good clinic will explain where they can be flexible without compromising safety.
Examples of areas where flexibility sometimes exists include:
Examples of areas that should be treated as non-negotiable for safety include:
When low-cost advertisements omit discussion of these categories, ask follow-up questions. A clinic that can’t explain how they maintain safety at a low price may not be the best fit for long-term outcomes.
Some clinics advertise mini dental implants as a lower-cost alternative in selected situations. In Spanish-language markets, specialized mini-implant providers (for example, those described by sites like Union City Mini Dental Implants) often focus on cases where the replacement area is limited.
From an expert viewpoint, mini implants may be appropriate in specific clinical contexts, but they are not universally “cheaper and better.” Selection should be based on:
It can help to understand how “mini vs standard” discussions typically map to clinical differences. Mini implants are often considered for situations where traditional implants and restorations might require more invasive surgical planning or when patients need a removable or less complex prosthetic solution. Standard implants usually offer more versatility and have different loading considerations. But “mini” doesn’t automatically mean “easy” or “risk-free.” The wrong selection can lead to failure or the need for conversion to a different restoration strategy.
Therefore, if you are considering any “low-cost” implant pathway, ask directly whether mini implants apply to your anatomy and bite mechanics, and how the clinic ensures stable good function.
Questions you can ask include:
Remember that affordability is not only the initial procedure cost. It’s also the likelihood that you’ll need additional treatment within a few years.
Use this list during consultations—whether you are researching Mismile Sheffield, a clinic in the United States, or a Spanish or Portuguese-speaking provider:
To make the checklist even more effective, bring a notebook or digital note and ask the clinic to answer each question in plain language. Also ask for copies of documents so you don’t rely only on memory. Many cost misunderstandings happen because verbal explanations get lost or simplified.
Additional “contract-level” items to request:
Finally, ask how they handle clinical reassessment. For example: “If during surgery you find bone quality different than expected, what steps do you take, and will I be informed before proceeding?” Transparency at this stage can prevent unexpected billing and reduce stress.
“Mismile Sheffield” may be a brand, marketing label, or local point of reference used by patients during searches. It should be treated as a starting point to identify a clinic or program. Always verify the actual provider’s clinical credentials, treatment planning process, and the details of what the quoted package includes.
If you see a “Mismile Sheffield” mention, you can reduce ambiguity by asking for the clinic’s full name, address, registration details, and whether the surgeon and prosthodontic lab are clearly identified. Then request the itemized treatment plan.
In many offers, “low cost” can mean implant surgery and associated planning are priced lower than average, but restoration stages (abutments and crowns/bridges) may be billed separately. The only reliable way to compare is to ask for a written itemized scope.
In some cases, “low cost” may include only implants and basic cover of surgical follow-ups, while prosthetic components and maintenance are excluded. In other cases, a low package may include interim temporaries but limit the number of adjustment visits. That’s why a detailed breakdown matters. If possible, ask the clinic for a “full treatment cost” estimate and a list of potential additional charges.
Not fully. Implant-only estimates represent one component of the overall treatment. For realistic budgeting, ask for the combined cost of the implant procedure plus the prosthetic restoration and any additional surgery (such as bone grafting) if needed.
A practical budgeting method is to compute three scenarios:
This approach helps you understand the range of financial risk instead of being surprised later.
Sometimes, but travel changes follow-up logistics. You should plan for aftercare, possible complications, and coordination with local dentists after you return. Reliable clinics and transparent paperwork are essential when distance is part of the plan.
When you consider travel, also remember non-clinical costs: flights, accommodation, time off work, medications, and possible additional visits if something doesn’t heal as expected. Even if the implant-only surgery is cheaper, the total value may change depending on travel and follow-up requirements.
Language support can improve clarity during consent, aftercare instructions, and risk discussions. However, communication does not replace clinical quality. You should still evaluate imaging quality, treatment planning, and restoration workflow.
In addition to language, consider cultural and practical clarity: does the clinic align instructions with your daily routine and ability to attend follow-ups? A provider that explains in your language but can’t accommodate your scheduling needs may still create risk.
Compare them by clinical scope, not by headline price. Ensure you’re comparing the same number of implants, similar materials, similar restoration types, and similar follow-up commitments.
If quotes differ in restoration type or number of implants, treat those differences as clinical design choices and ask for justification. You can also ask for “one-to-one equivalency”: “If we use the same restoration material and number of implants, how would the quote change?” Even if you can’t fully equate them, the process will reveal which quote is truly more comprehensive.
They may be less expensive in selected cases, but “cheaper” depends on your anatomy, loading demands, and prosthetic plan. A clinician should determine if mini implants are appropriate for your needs.
Mini implants can sometimes reduce the need for extensive augmentation in certain anatomical situations, but they can also involve different maintenance or prosthetic designs. The right question is not only “are mini cheaper,” but “are mini the best value for my specific case and risk profile?”
In some markets, dental plans or insurance can reduce out-of-pocket costs, but coverage varies. If insurance is relevant, ask the provider how to document treatment needs and what plan types are compatible with implant procedures.
Also ask whether your plan requires you to use specific providers or labs. If so, compatibility may affect affordability in practice.
Low-cost pathways are often compatible with responsible clinical standards, but they usually assume specific conditions:
If a low-cost offer cannot explain these elements clearly, the “savings” may be illusory—shifted into later billing or increased risk of additional intervention.
To understand “requirements,” think about what must go right at each stage. For implant success, the following areas are often crucial:
If a low-cost clinic provides minimal guidance around any of these areas, you should ask why. It may be that they only treat low-complexity cases. Or it may indicate a mismatch between your needs and their workflow model. Either way, clarification is essential before you sign.
Searching for Mismile Sheffield alongside “low-cost dental implants” usually signals a patient’s need to balance affordability and quality. The professional way to accomplish that balance is to treat low-cost as a starting point for research, then demand clarity: itemized scope, appropriate diagnostics, and a restoration plan that matches your functional and aesthetic needs.
Across English-speaking and multilingual communities, the same principle holds: the safest cost reduction comes from aligning clinical strategy with eligibility—rather than from skipping steps. When you do that, you can compare providers more reliably, whether you consider clinic care in your region or structured care pathways informed by reputable dental education resources.
Before you commit, consider one final practical check: can you describe your implant plan in detail—how many implants, what imaging is used, what grafting is expected, what restoration will be placed, and what follow-up schedule applies? If you can’t, the decision is too ambiguous for “affordable” planning. A good clinic will help you reach that level of understanding without pressure.
1) The above information comes from online resources, and the data is as of October 2023. 2) Dental implant prices are for reference only and may vary by region, clinic and doctor.
- https://dentalviews.com/low-cost-dental-implants/
- https://www.atlanticdentalgrp.com/
- https://www.dentavacation.com/
- https://rockvilledentalarts.com/es/
- https://unioncityminidentalimplants.com/es/
- https://www.cigna.com/es-us/knowledge-center/guide-to-dental-implants
- https://www.rubiodonto.com.br/
- https://odontologiavelasco.com.br/
- https://dentalvidas.com.br/
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Affordable Full Mouth Dental Implants Near You
Discover options for affordable full mouth dental implants, including clinical trials and local dental services that offer cost-effective solutions.
Understanding Full Mouth Dental Implant Prices
Explore the costs and factors influencing full mouth dental implants for seniors and others.
Comprehensive Guide to Dental Implants
This comprehensive guide delves into the intricacies of dental implants, providing a global perspective with a special focus on Implantswiss. Dental implants, a pivotal advancement in restorative dentistry, offer solutions for missing teeth, aiding in oral health and functionality. This article navigates through cost-effective solutions, global pricing comparisons, and the role of Implantswiss in elevating dental care standards internationally.

Affordable Dental Implants Near You
Discover low-cost dental implants and quick solutions to fix your teeth with full mouth options available near you.
Understanding Dental Implant Prices and Options
Explore dental implant costs, funding, and full mouth options for a confident smile in 2025.
Affordable Dental Implants Near Me: Your Guide
Discover affordable dental implants, funding options, and fast solutions for fixing your teeth near you in 2025.
