This guide explains how to run an OpenEMR Demo and evaluate whether an electronic medical record system fits clinical workflows. It presents neutral background on EMR evaluation, common demo features, and how to assess usability, configuration depth, and security expectations across healthcare environments.
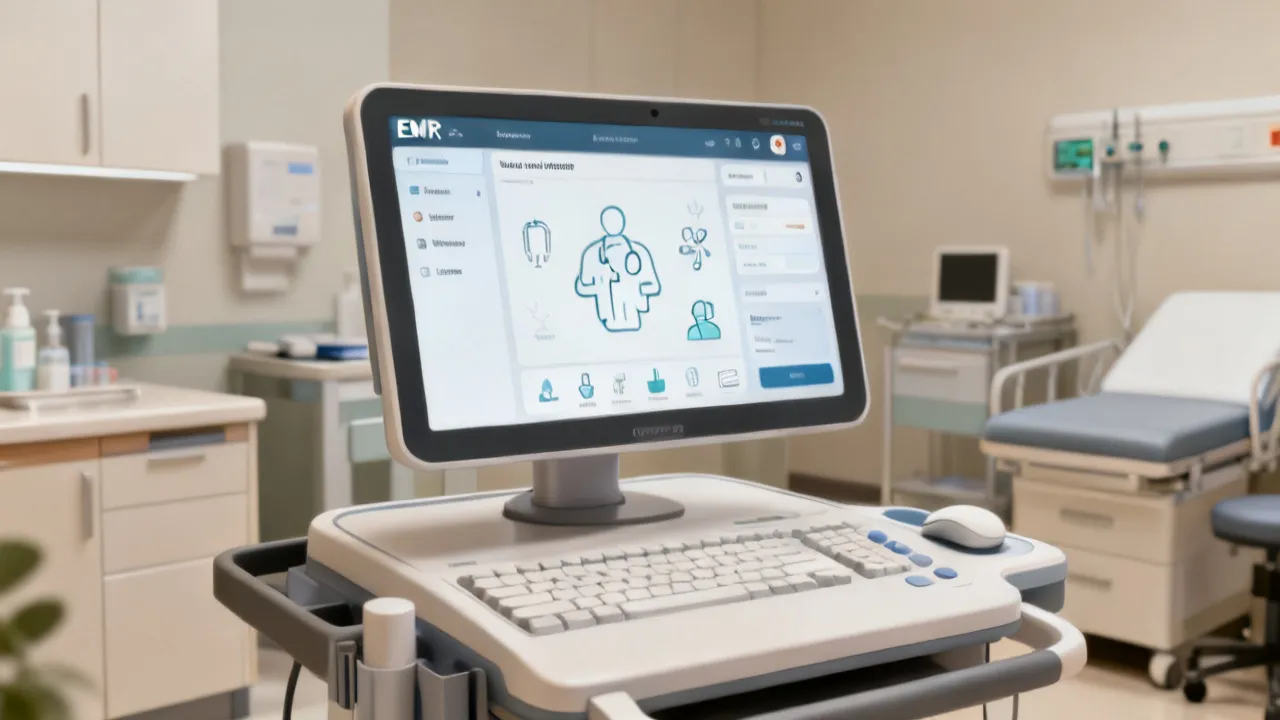
An OpenEMR Demo is very valuable when you treat it like a structured test of real clinical workflows—registration, documentation, orders, and reporting—rather than a quick tour of screens. The goal is to confirm that the software’s configuration options match how your team works today, and that the data model supports future reporting and interoperability needs.
In an industry where clinical teams rely on EMR data for safe care delivery, an EMR demo should answer practical questions: Can staff find the right fields quickly? Does the system support your specialty documentation patterns? How does it handle user roles, audit trails, and backups? These points matter more than marketing promises because they affect daily usability, clinical safety, and operational continuity.
Importantly, the demo is not only about “what the system can do.” It is about what your organization will realistically be able to implement with the timeline, the budget, the internal skill set, and the operational constraints you actually have. A great-looking interface that hides configuration gaps or workflow mismatches can still create significant risk when you go live.
Therefore, before any rollout, you should approach the OpenEMR Demo as an evidence-gathering exercise. You are validating workflow fit, checking for documentation completeness and data integrity, confirming role-based access and auditing, and identifying the implementation work needed to reach your clinical and operational goals.
When organizations request an OpenEMR Demo, they typically want clarity on functionality. However, demos frequently fail to reveal the “edge cases” that surface during live operations—like multi-provider documentation, time zone handling for appointment schedules, or order dependencies. A careful evaluation framework helps you uncover gaps early, when changes are still low-cost.
Many demo agendas are optimized for showmanship. They emphasize a few “happy path” workflows and minimize friction points. In a real clinic, friction points are exactly what can threaten safety, compliance, and staff productivity. For instance, a demo might show how a clinician creates a note, but not show how the note behaves when multiple diagnoses, multiple problem lists, addendums, missing required fields, or late updates occur.
In addition, demos often overlook operational realities such as scheduling and cancellation workflows, handling of no-shows, rescheduling across time zones, patient record merging, dealing with incomplete demographics, or working with partially available clinical data from integrations. Even if your clinic believes these edge cases will be rare, your evaluation should still verify how the system behaves when they do occur.
From an implementation perspective, the top demos simulate a typical day in your clinic or health network: patient intake, clinical note creation, medication reconciliation, and the generation of a usable summary. If the demo cannot represent your core journeys, you’re evaluating the interface rather than the system’s operational fit.
To avoid that trap, insist on structured scenarios that reflect your actual work. Don’t just ask the demo team to “show e-prescribing.” Ask them to demonstrate the precise end-to-end process your clinicians and staff will follow, including prerequisites like patient demographics, insurance data, formulary selection (where applicable), medication history availability, and clinical sign-off behavior.
To make your OpenEMR Demo actionable, run it like an audit of workflow compatibility. Below is a structured approach that emphasizes measurable outcomes over subjective impressions.
Even a strong OpenEMR Demo can differ from production conditions. Common divergence points include:
To catch these divergences early, require that the demo environment be configured to reflect your intended roles and templates as closely as possible. If the supplier cannot configure the demo fully, ask what the gap is and what work would be needed to close it. In particular, ask for screenshots or configuration artifacts that explain how a template becomes a structured form and how it enforces required fields.
Also, pay attention to “invisible workflows.” For example, a demo might show a clinician entering data but not show the downstream effect on billing, care management workflows, or scheduled follow-up tasks. In real life, a clinician might complete documentation, but if billing rules or coding workflows don’t see the expected structured fields, the organization will experience delays or errors.
Finally, consider the human factor. Demos often show ideal user behavior in a training environment. In production, users will differ in speed, confidence, and familiarity with the EMR. A practical demo includes at least one “realistic” attempt by your users, with minimal coaching, to measure learnability and workflow clarity.
Because OpenEMR Demo readiness depends on both the platform configuration and the support model, supplier discussions should go beyond features and include delivery processes. A useful supplier conversation covers:
Instead of asking only “Can you do it?”, ask: “How will you demonstrate this in the demo, and what artifacts will you provide for verification?” That framing reduces ambiguity during procurement.
It can also help to ask for specific examples of what documentation and evidence the supplier provides. For instance, ask whether they provide a template inventory, configuration guide, role matrix, or a report definition catalog. Those artifacts often determine how smoothly you can maintain the EMR after go-live.
Additionally, ask how training is delivered and measured. Many rollouts fail not because the EMR cannot do something, but because training does not match real tasks. Ask whether training includes guided practice on your exact templates and order sets, and whether it includes “day-2 operations” such as handling missing data, performing late chart updates, correcting errors, and generating reports.
Ask too about how the supplier handles clinical content governance. For example, if your organization changes diagnosis coding preferences, medication reconciliation rules, or structured question sets, you’ll need a process for updating templates safely. A mature implementation partner will describe how they test changes and how they communicate updates to users.
To evaluate an EMR accurately, you must consider local clinical practice patterns and operational norms. In many healthcare environments, workflows differ by staffing models, documentation habits, and how patient intake information is captured at the front desk.
For example, in clinics serving patients across different cultural backgrounds, clinicians often need documentation structures that support consistent symptom reporting and medication reconciliation practices. During an OpenEMR Demo, encourage the supplier to show how the system supports structured documentation rather than forcing clinicians to rely on affordable-form text.
Also consider the communication style used in your region—some organizations prefer concise visit notes; others require more detailed structured documentation for compliance and continuity of care. Your demo agenda should reflect these realities.
Localization is not only language. It includes how your clinicians think about diagnoses, how your organization tracks immunizations, whether you need specific forms for certain clinical programs, and which coding or documentation standards you follow. A demo that uses generic templates may hide gaps that only become visible once your teams attempt to use structured fields in their real workflow.
Additionally, consider the patient identity and consent workflows required in your jurisdiction. If your environment has strict rules about consent, record sharing, or restricted data access, the demo should show how those restrictions manifest in the UI and in audit logs. If these features are not demonstrated, ask for a configuration walkthrough or evidence from prior implementations.
Time-related behavior is another localization issue. Scheduling often involves time zones, daylight saving adjustments, appointment slot rules, and special scheduling types (telehealth appointments, home visits, or procedures). During the demo, verify that date/time inputs and displays align with what your team expects, including how times are stored and presented across user roles.
The following comparison table reframes what you should evaluate during procurement. It is not a price claim and avoids unverifiable figures. Instead, it outlines typical conditions and requirements you can ask either the supplier or your implementation partner to confirm.
| Evaluation Option | What It Shows in an OpenEMR Demo | Top Fit When | Conditions / Requirements to Confirm |
|---|---|---|---|
| Workflow-centered demo | Registration, encounter notes, orders, results review, and summaries | Your team wants evidence of operational fit | Provide sample scenarios aligned to your specialty and patient flow |
| Role-based demo | Front desk, clinical roles, and administration permissions in action | Multiple user types must coordinate safely | Demonstrate permissions, auditability, and access timing per role |
| Reporting and analytics demo | Visit metrics, documentation completeness views, and operational dashboards | You need measurable governance and quality checks | Clarify report definitions, data fields used, and export options |
| Integration and data exchange demo | Incoming results handling, interface considerations, and mapping logic | You rely on labs, imaging, or external services | Specify integration responsibilities and configuration steps |
| Migration planning walkthrough | Data mapping approach for legacy charts and structured elements | You must move existing records without losing clinical context | Confirm mapping method, data quality checks, and validation process |
When deciding between demo options, avoid treating these as separate “days.” In reality, workflows connect everything: documentation affects reporting, reporting depends on structured data objects, and integration depends on the same data model. If the supplier offers only isolated demos (for example, one day for UI and another for integration), you should request an end-to-end integrated walkthrough that shows how one workflow generates the data used in reports and downstream tasks.
The phrase “OpenEMR Demo” can appear in procurement contexts where organizations want clarity on cost drivers. In practice, EMR pricing is commonly influenced by factors such as:
Because price lists can vary by region, partner, and implementation scope, the very objective method is to request a written estimate with line items tied to demo-confirmed requirements (for example: “configure role-based access,” “build specialty note templates,” “prepare import mapping,” and “validate reporting definitions”).
To make pricing more meaningful, tie costs to deliverables and acceptance criteria rather than to vague effort estimates. For example, you can define deliverables such as:
Once you tie costs to deliverables, procurement becomes less about negotiating price and more about negotiating scope quality. That reduces the risk of scope creep and helps ensure that the rollout matches what was demonstrated during your evaluation.
In healthcare IT, EMR evaluations are closely tied to patient safety, data integrity, and privacy protections. The U.S. Office of the National Coordinator for Health Information Technology (ONC) has published guidance emphasizing how electronic health record capabilities support clinical workflow and information exchange; while this is not a direct endorsement of any specific vendor, it reflects the broader policy focus on functionality, usability, and interoperability planning. For general reference, see ONC’s Health IT resources and documentation on EHR capabilities and implementation considerations.
Additionally, international healthcare quality and safety discussions often emphasize that technology adoption must be supported by training, governance, and careful configuration—especially for clinical documentation and order entry workflows. The strongest procurement processes therefore treat the EMR demo as the starting point for structured requirements gathering.
Risk controls are not limited to cybersecurity. They include clinical risk controls such as:
When you run the OpenEMR Demo, ask how these risk controls are addressed in the configuration and operational model. For instance, how does the system prevent a clinician from signing a note without completing required structured fields? How are corrected errors handled? What does the audit log show and how accessible is it to administrators or compliance officers?
After your OpenEMR Demo, consolidate findings into requirements that can be verified. This reduces the chance of later disputes about “what was shown.” Use a checklist format aligned to the inverted pyramid principle: decide what matters very, document it clearly, and confirm it with the supplier.
Consider splitting requirements into categories: clinical workflow requirements, data model requirements, security and audit requirements, reporting requirements, and integration requirements. Doing so ensures you don’t miss important details just because a demo team focused on an area you didn’t initially prioritize.
To strengthen the checklist, include acceptance criteria for each requirement. For example:
When requirements are written with measurable acceptance criteria, you can validate progress during implementation—not only at the end of a project.
To keep evaluation evidence-based, align demo expectations with commonly recommended healthcare IT practices. Reliable references include:
Always request vendor-specific documentation for actual security controls, audit logging behaviors, and update policies.
While general standards help you ask better questions, the demo is your only chance to observe real behavior in a controlled environment. Treat the demo as a behavioral validation step, while vendor documentation provides deeper assurance. If the supplier cannot show behavior in the demo (for example, audit log details), require a demonstration using the actual configuration you plan to adopt—or require evidence from previous deployments.
In addition, ask about operational security beyond configuration. For example: how are passwords managed and rotated? Are sessions timed out and reauthenticated for sensitive actions? Is the demo environment representative of the planned production hardening? If not, ask what will change between demo and production.
An OpenEMR Demo is used to evaluate whether the electronic medical record system can support your clinical and operational workflows. The very useful demos test registration, documentation, order handling, results viewing, and reporting under role-based access conditions.
It is also used to identify the implementation work you will need before go-live. A strong demo surfaces configuration gaps, training needs, and integration considerations early enough that you can plan changes without disrupting your rollout timeline.
Workflow evaluation is more important. A well-designed interface matters, but the real question is whether the system supports your day-to-day processes without risky workarounds. A demo should include role-based tasks and realistic scenarios.
In many cases, teams over-index on screen design because screen design feels tangible. Yet the workflows—how information is captured, validated, reviewed, and used later—are what determine clinical safety and operational performance.
Ask for sample patients and sample orders that match your specialty needs, plus edge cases you expect in live use. Also, request time estimates for key tasks (e.g., note creation) and confirm how permissions affect each user role.
Additionally, run a short hands-on segment with your real users. Provide them with a scenario and ask them to complete it with minimal guidance. If they require extensive coaching that the supplier cannot replicate, it may indicate a learning curve or documentation design issue that will affect adoption.
Ask how configuration will be handled, what responsibilities are on your side, how audit logs work, what training is provided, and how integrations (if needed) are planned. You should also ask for examples of reports you want to monitor and how those reports are defined.
Bring your own workflow questions. For example, if your clinicians regularly do medication reconciliation at each encounter, ask the demo team to show exactly how they capture current meds, compare them against a history, handle changes, and generate a summary that supports continuity of care.
You should discuss migration early. Even if the demo does not perform a full import, you can evaluate whether the supplier has a mapping approach, validation steps, and a method to handle data quality issues from legacy systems.
If migration is planned, request clarity on how the supplier handles missing or inconsistent values, how they prevent duplicate patient identities, how they validate clinical record completeness, and how they reconcile coding structures and free text fields from legacy systems.
Request specific reporting examples tied to your goals, such as documentation completeness checks, operational visit metrics, and exports for audits. Confirm whether reporting definitions rely on configurable templates or manual processes.
Also evaluate whether reports are transparent and maintainable. If you can’t explain the logic behind a metric, you may not be able to trust it for quality improvement or governance decisions.
A demo can show parts of role-based access and audit visibility, but security readiness requires additional evidence such as security documentation, operational policies, and configuration guidance. Treat demo observations as indicators, not final proof.
To strengthen assurance, ask for documentation and evidence of backup procedures, recovery testing, vulnerability management processes, and configuration hardening practices. Also ask how access changes are managed and how audit logs can be used for compliance investigations.
No. A demo demonstrates capability under controlled conditions. Implementation involves configuration, training, governance, migration planning, and ongoing support. Your procurement should separate demo verification from production delivery scope.
A helpful way to ensure this separation is to define acceptance criteria for implementation deliverables that are distinct from what is shown in the demo. For example, your demo may show a sample template, but implementation acceptance may require that your organization’s final templates, roles, integrations, and reporting definitions are validated through test scripts.
An OpenEMR Demo should be structured, evidence-driven, and aligned with your very critical workflows. When you evaluate usability, role-based access, order and results handling, reporting readiness, and integration planning in a single cohesive test, you reduce implementation risk and improve decision quality.
If you approach the demo as the start of requirements discovery—not a marketing preview—you’ll be better positioned to select an EMR environment that supports safer documentation, clearer clinical coordination, and dependable operational reporting over time.
To maximize the value of your evaluation, remember that the most important “check” is not whether the demo system looks impressive, but whether it behaves correctly under the workflows your staff will actually use. When your organization demands scenario-based evidence, clear responsibilities, and measurable acceptance criteria, the OpenEMR Demo becomes a practical decision tool that supports safer, more predictable go-live outcomes.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading


Understanding the Concept of Ibiaeon
Dive into the groundbreaking concept of Ibiaeon, a theoretical model that combines technological advancements with philosophical perspectives. Ibiaeon represents a unique intersection where innovation meets ethical considerations, aiming to offer sustainable solutions for future societal challenges. This guide presents a deep analysis of the possibilities and implications associated with Ibiaeon.

Understanding the Sage Cte Platform
Sage Cte is a powerful software offering comprehensive solutions for businesses across various industries. This article delves into its capabilities, exploring its integration with different systems, cost implications, and the significance of choosing the right supplier. By understanding Sage Cte, businesses can make informed decisions for optimal operational efficiency and competitive advantage.

An In-Depth Look at Salesforce
Salesforce is a transformative cloud-based customer relationship management (CRM) platform that empowers businesses to streamline their sales, service, and marketing efforts. Known for its robust suite of tools and global reach, Salesforce has become an industry standard in CRM solutions, providing businesses with unparalleled insights and automation capabilities essential for growth and customer retention.
Seamless Integration of Sagepay and Salesforce
This guide highlights the integration of Sagepay with Salesforce, emphasizing the importance of harmonizing payment processing with customer relationship management. Sagepay offers secure online payment solutions, while Salesforce provides comprehensive CRM services, both popular among businesses seeking efficiency. Explore how they complement each other for enhanced business functionality.

Plansource BambooHR: Expert HR Platform Comparison Guide
Plansource BambooHR helps organizations standardize HR workflows with modern recruiting, onboarding, and people analytics. This guide explains what the keywords typically refer to in HR technology contexts, outlines how businesses evaluate these platforms, and provides an expert comparison framework so HR leaders can make informed sourcing decisions based on requirements, implementation scope, and total cost considerations.

Integrating Sagepay with Salesforce
Integrating Sagepay with Salesforce streamlines business operations by combining sophisticated CRM capabilities with a secure payment gateway. This fusion allows businesses to efficiently manage customer relations and transactions within one seamless framework. Sagepay ensures secure and swift payments, while Salesforce aids in comprehensive customer relationship management, enhancing overall operational productivity and customer satisfaction.
