Alelo Barueri guide helps you understand how health and care-related benefits are typically assessed, managed, and used in nearby Brazil-focused contexts. It also explains, in an objective way, what “Alelo” generally refers to in the benefits ecosystem, and how “Barueri” functions as a local reference point for services, suppliers, and operational expectations.

When people search for “Alelo Barueri,” they are often trying to confirm how a benefits or care program is handled in a nearby setting—whether that means eligible services, partner providers, coverage rules, or operational expectations. As an industry-oriented approach, the first step is to verify the exact scope of the offering you’re evaluating (for example: healthcare-related access, reimbursement logic, provider network rules, and any administrative requirements). This matters because “Alelo” can be associated with different benefit use cases, while “Barueri” typically signals where residents and companies expect those services to be accessible and administratively workable.
Below, you’ll find an objective framework to help you evaluate the meaning of “Alelo Barueri” in a responsible and auditable way—without relying on rumors or unclear claims. If you’re a consumer, HR manager, or procurement professional, the sections on requirements and decision criteria are designed to reduce uncertainty and support consistent choices.
In everyday use, the phrase “Alelo Barueri” combines a brand-like term (“Alelo”) with a locality marker (“Barueri”). In a business context, this often reflects one of the following:
Importantly, the phrase itself doesn’t automatically specify the exact program configuration. Therefore, the key objective is to confirm the program’s documented rules before making assumptions.
Even when the same overarching benefit model exists across Brazil, local conditions tend to affect how smoothly beneficiaries can use it. In nearby contexts like the Barueri area, practical differences may include:
From an industry standpoint, these details often determine whether a program feels “usable” versus “complicated,” regardless of the brand name used in search queries.
It’s also worth noting that “nearby” is not just geography; it’s operational proximity. A clinic might be geographically close but administratively disconnected from a specific contract configuration, meaning the beneficiary’s experience depends on how the program’s verification and billing flow is executed at the point of service. This is why a locality keyword like Barueri can become a clue—yet not a guarantee—about how easily the process will run.
In healthcare and benefits ecosystems, the very reliable evaluations focus on process transparency rather than marketing language. An expert review typically considers:
1) Eligibility logic
How does the program decide what qualifies? Look for clear definitions of covered categories, service limitations, documentation requirements, and any exclusions. “Covered” and “approved” should not be treated as the same thing; approvals often depend on pre-authorization rules.
2) Provider participation rules
Does your clinic or preferred professional participate? If provider participation changes over time, you need a mechanism to verify status before appointments. Procurement and compliance teams also care about contract terms and quality obligations.
3) Operational workflow
From scheduling to payment, how does the program handle verification and settlement? Clarity here affects both patient experience and provider revenue predictability.
4) Administrative requirements
What documents or steps are required at the time of service? Missing requirements can lead to delays, denials, or partial payments.
5) Auditability and complaint resolution
A well-run program offers a documented path for disputes, billing questions, and escalation. That reduces the risk of unresolved issues that degrade trust.
6) Data handling and privacy expectations
Even when the program is “local,” it may require identity verification or the exchange of patient information between provider and program operator. In a mature framework, beneficiaries should have transparency about what information is collected, who can request it, and how disputes can be pursued without unnecessary exposure.
7) Service continuity considerations
For ongoing treatments (not just one-off services), evaluate whether the program supports continuity—meaning it can handle multi-step care, referrals, and follow-up documentation without repeated friction. A program might work for a single consultation but fail operationally for longer care paths if pre-authorization and billing workflows aren’t aligned.
8) Change management
Provider networks can change. Policies can be updated. Programs should have a mechanism for notifying users and providers about changes to eligibility rules, pricing, or documentation steps. If you can’t find a stable version of the rules or a way to confirm “current” coverage, the risk of disruption increases.
You requested integration of “price information” and “supplier details,” but no concrete numbers or named supplier entities were provided. In professional decision-making, that’s a good reminder: any “price” you encounter for a care or benefits use case should be tied to a verifiable quotation, a contractual schedule, or a documented fee policy.
Here are responsible ways to confirm pricing and supplier-related facts in Alelo Barueri type evaluations:
This method ensures you base decisions on operational facts rather than approximations.
To make this even more robust, treat pricing as a chain of decisions rather than a single number. For example: the cost you’re quoted at scheduling might differ from the final amount if pre-authorization is required or if the provider submits billing in a category that the program later determines is not applicable. An “itemized estimate” should ideally identify which line items depend on eligibility confirmation, which items depend on medical or administrative approvals, and which items are independent of those decisions.
In supplier terms, “supplier details” can include more than the clinic name. It can include the legal contracting entity, the billing entity, and the provider credentialing status. For an audit-ready evaluation, ensure you know who is expected to bill, what category they bill under, and which documentation they must include for approval. This reduces the risk of “we billed correctly but the program’s rules treat it differently,” which is a common operational failure mode in benefits ecosystems.
If you are an HR manager or procurement professional, you might also want to request:
While the term “Alelo” is often mentioned in Brazilian benefits conversations, the exact service category can vary by employer plan and by contract structure. Objectively, people typically relate such brands to one or more of the following:
Because “Alelo” can appear in multiple program contexts, you should confirm the specifics of your plan or the program you’re considering in the Barueri area.
In practical terms, two beneficiaries might both search “Alelo Barueri” but actually be looking for different things. One might want to use a provider network for consultations; another might want reimbursement for specific services already received; another might be investigating an employer-supported benefit category with a separate administrative flow. The local term can blur these differences unless the user verifies the written rules tied to their employment or enrollment configuration.
To support your decision, use the framework below to compare what you should verify. (No links are included, as requested.)
| Assessment area | What to verify | Typical requirement/condition | Why it matters |
|---|---|---|---|
| Eligibility scope | Which care categories qualify under your plan | Documented coverage rules and definitions | Prevents surprise denials and service mismatches |
| Provider participation | Whether your chosen clinic/professional participates | Valid authorization for the relevant service category | Ensures the workflow actually works at appointment time |
| Authorization rules | Whether pre-approval is needed | Procedure documentation and turnaround time commitments | Avoids scheduling delays and incompatible billing |
| Documentation | What documents beneficiaries must present | ID/plan credentials and any supporting forms | Reduces processing errors and incomplete claims |
| Pricing and settlement | How charges are calculated and settled | Itemized estimates, fee schedules, and settlement timelines | Clarifies what you pay and what the program handles |
| Dispute resolution | How denials or billing questions are reviewed | Documented escalation path and response commitments | Protects good trust and operational continuity |
Sources (background references): This article uses general top-practice reasoning common in healthcare administration and benefits governance. For formal regulatory context in Brazil, consult official guidance from relevant government and oversight bodies (e.g., health and consumer protection authorities) and program documentation provided by the plan administrator or employer contract. For benefits administration concepts such as network management, eligibility governance, and billing workflow transparency, refer to healthcare operations literature and healthcare compliance standards published by recognized professional organizations.
In addition to the background references, it is often useful to align evaluation practices with internal governance norms: HR policies for employee benefits, procurement standards for vendor assessment, and compliance checklists that require auditable evidence. Those internal frameworks can be more important than public-facing claims when you want consistency and traceability.
Use this sequence to keep your evaluation consistent—whether you’re selecting a provider network, verifying eligibility rules, or reviewing procurement decisions for a company.
Step 1: Identify the exact plan or program reference
Don’t rely only on “Alelo Barueri” phrasing. Confirm whether the program is tied to a specific employer contract, public/private plan, or internal policy. Request the plan’s written scope.
Step 2: Confirm provider participation for your service category
Ask your preferred provider (or check the provider’s billing desk processes) to confirm participation for the specific type of care you intend to receive. A clinic may participate for one service category but not another.
Step 3: Validate eligibility requirements before scheduling
Make sure you understand what you must present at appointment time. If pre-authorization is required, confirm who submits it (patient, provider, or plan administrator) and the required lead time.
Step 4: Obtain an itemized estimate
Ask for a breakdown of procedure/service categories, the expected administrative steps, and how settlement will occur. If a quote includes multiple service items, clarify which items depend on approvals.
Step 5: Ask about billing timelines and settlement method
Determine whether charges are processed directly, reimbursed later, or split. Confirm expected turnaround times for approvals and final settlement.
Step 6: Review dispute and escalation pathways
If anything goes wrong—partial payment, denied authorization, or documentation mismatch—know where to send the request and what timeline you can expect for review.
Step 7: Document your decision
Keep copies of plan scope, approvals, and estimates. This supports continuity, especially if multiple beneficiaries use the program.
Many users focus on provider availability and assume that once they can find a clinic, the program will function smoothly. However, operational reliability depends on subtler details. The following questions can help you catch risk early, especially for services that require multi-step workflows.
1) Are there service-specific documentation requirements?
Some categories may require referrals, clinical notes, proof of prior treatment, or specific forms. Ask whether your service category has unique documentation steps beyond standard ID and plan credentials.
2) What happens if the service outcome changes?
For example, the intended procedure might be modified at the time of care. Clarify how billing is handled if the clinical outcome differs from the initial estimate—does it trigger a new pre-authorization, or does it fall under an adjustment process?
3) Is there a time limit for submitting claims or reimbursement requests?
Many programs enforce submission windows. If you miss deadlines, the program may deny or reduce coverage. Confirm these timelines in writing.
4) Does the program cover ancillary services?
Ancillary services (such as lab tests, imaging, anesthesia components, or follow-up evaluations) can materially affect cost. Ask which ancillary items are covered for your category and whether they must be billed separately.
5) Can you verify eligibility in advance?
Some programs allow pre-checks or eligibility verification before the appointment. If available, it can reduce the risk of arrival-day denials. Ask whether an eligibility verification step exists and how it is requested.
6) Are there ceilings, limitations, or frequency rules?
Coverage might be limited by frequency (e.g., maximum number of visits per month) or by annual ceilings. Identify these rules early to avoid “works once, fails later” scenarios.
7) Are there requirements for network referrals or second opinions?
Certain care pathways require referrals or specialized program workflows. Confirm whether these exist and who is responsible for initiating them.
To operationalize that checklist, many teams also add a “proof of work” approach: verify eligibility in writing, request an itemized estimate, and keep a record of authorizations. In the real world, claims disputes are frequently resolved faster when evidence is complete and chronological. If a beneficiary or HR team can show what was approved, by whom, and under which category definition, it becomes easier to correct errors.
One of the most common misunderstandings is the difference between a clinic’s general willingness to accept patients and the specific authorization required under your program. A clinic may say they work with “Alelo” generally, but the question is whether they are authorized under your exact plan configuration and for your exact service category.
In an auditable evaluation, you should aim to confirm at least three layers:
Clinics sometimes participate for some categories but not others. They also sometimes update their participation status, add new service lines, or modify billing processes. If you’re booking a service that’s not routine—such as specialized therapy, diagnostic procedures, or a course of ongoing care—ask for confirmation specifically for that pathway. In many systems, what matters is the category definition used for billing rather than the broad label that users commonly see.
Authorization rules are often treated as a single concept (“do I need approval?”). But for operational reliability, authorization has at least two aspects:
From the patient or beneficiary perspective, the risk is booking without clarity and then arriving to a denial or a delay. From the provider perspective, the risk is performing work without adequate billing authorization—potentially leading to unpaid balances. The safest approach is to confirm in advance whether approval is needed and how it will be handled.
Ask questions like:
These questions might feel detailed, but the detail is the point: benefits ecosystems are operational systems, not just informational websites. When you understand the workflow, you’re less likely to encounter “surprise denials” and can better manage scheduling decisions.
Documentation is not merely a list of required items; it is also about formatting, completeness, and the timing of submission. Many denials occur because the submitted documentation is missing a key element, is submitted in the wrong format, or is submitted under a claim category that doesn’t match the service provided.
To manage documentation risk, ask for guidance in advance about:
For HR teams, a useful step is to standardize documentation processes across employees. If multiple employees use the same program, inconsistent submission habits can create inconsistent outcomes. Internal HR communications can instruct beneficiaries on required steps. This reduces variability and increases the probability that claims are processed successfully on the first attempt.
“Price information” is often presented in a way that feels straightforward, but in benefits workflows it can be complex. The final cost can depend on eligibility verification, authorization outcomes, and provider billing category definitions.
To make pricing expectations auditable, you want a breakdown that distinguishes:
Even when you can’t get exact final numbers upfront, the process can still be managed. Request:
If the program uses reimbursement, ask whether reimbursement is capped and whether it reimburses the full provider charge or only an allowed amount. If the program uses direct payment, ask what the beneficiary’s responsibility is (copay, deductible, or remaining balance) and how that is communicated at the point of service.
Even well-run programs encounter errors. The key is how the system corrects them. Dispute resolution is a core part of “program reality.” When the process is clear, issues don’t escalate into extended delays.
When evaluating a program, look for evidence of a structured dispute process. Consider:
From a beneficiary standpoint, the goal is to avoid repeating the same submission steps multiple times. From an HR or procurement standpoint, the goal is to identify systemic issues—such as providers billing under the wrong category definitions or the program rejecting claims due to incomplete documentation requirements. If dispute data can be summarized and used for process improvement, the overall experience improves for everyone.
Many users evaluate programs using online information, but the “day-of-care” experience depends on workflow reliability at the provider site. You can reduce day-of-care risk by verifying operational workflow elements beforehand.
Consider these practical operational questions:
If you are scheduling and you don’t know how the workflow works, ask the provider what they typically request from beneficiaries. Providers usually have a practical understanding of what causes delays. Getting that information can prevent frustration and reduce the chance of missed appointments due to administrative issues.
When Barueri appears in search terms, it often acts as a proxy for local network density. A higher density can mean easier scheduling, but density can also vary by specialty. Some specialties might have strong provider presence in the area, while others might require longer travel.
Therefore, don’t treat Barueri as a blanket improvement. Instead:
In long-term treatments, network density matters even more because follow-up visits require consistent provider access. If follow-ups are likely to require multiple providers, you should evaluate how well the local network supports that entire pathway.
The meaning of “Alelo Barueri” is interpreted differently depending on the beneficiary’s role. A structured evaluation framework should reflect these role differences, because each role has different responsibilities and risk exposure.
For patients/beneficiaries: the main concerns are eligibility clarity, provider participation for the service category, documentation at point of care, and knowing whether costs are front-paid or reimbursed.
For HR managers: the main concerns are plan scope correctness, consistent employee communication, administrative workload, dispute escalation management, and vendor performance monitoring.
For procurement/compliance professionals: the main concerns are auditable contract terms, pricing schedules, network governance, dispute resolution SLAs, and the ability to verify and reconcile billing across providers.
As a result, your evaluation checklist should adapt. HR might prioritize written plan scope and internal comms; procurement might prioritize contract schedules and audit capabilities; beneficiaries might prioritize day-of-care steps and authorization handling.
When people say “supplier details,” they sometimes mean only the clinic. In benefits ecosystems, supplier details can include:
If you have disputes or delayed payments, these details matter because the troubleshooting must happen at the correct operational point. A beneficiary may talk to reception, while the claim correction is handled by a billing department. If you don’t know which contact is responsible, disputes can drag on.
People often encounter pitfalls when they rely on search results, forums, or second-hand claims. These pitfalls include:
To reduce these pitfalls, treat “Alelo Barueri” as a keyword that triggers verification steps rather than a final answer. The safest path is always: confirm scope → confirm provider participation → confirm authorization and documentation → confirm settlement mechanics → confirm dispute resolution.
It generally refers to how a benefits or healthcare-related ecosystem associated with “Alelo” operates in or around Barueri. However, the exact meaning depends on the specific plan contract and the service category you’re considering. Always verify the written program scope.
Ask the provider’s administrative or billing desk whether they are authorized for your specific service category under your plan. Participation can differ by procedure type and can change over time.
You can often obtain an itemized estimate, but the final amount may depend on eligibility verification and any required pre-authorization. Request itemization and approval conditions before the appointment.
Review the denial reason against the plan’s written eligibility rules, then use the program’s documented dispute or escalation path. Keep copies of approvals, estimates, and submitted documentation to support your request.
Local conditions can affect network availability, appointment scheduling, and workflow execution. However, the underlying eligibility and coverage rules typically come from the plan contract and documented policies.
Because benefits and provider networks depend on operational contracts, incorrect assumptions about provider status or fee settlement can lead to payment delays or partial coverage. Itemized estimates and authorization checks reduce those risks.
Minimize delays by submitting complete documentation, ensuring the claim category matches the provided service, and keeping proof of submission. Confirm the program’s submission deadlines and accepted formats before you send anything.
That situation usually indicates a mismatch between the broad acceptance claim and the specific service category, authorization requirement, or documentation details. Use the denial reason to identify the exact rule or missing element, then escalate through the program’s dispute path with the supporting evidence.
HR can track issue types (authorization delays, documentation errors, category mismatches), collect examples, and request process improvements from the program administrator. Procurement can use audit-ready evidence to renegotiate operational expectations, clarify fee schedules, and tighten network governance requirements.
Not necessarily. While local networks can reduce scheduling friction, authorization turnaround times are typically determined by the program’s internal review workflows. Confirm approval timelines in writing for your service category.
In a nearby context, “Alelo Barueri” is top approached as a starting point for research into scope, eligibility, provider participation, pricing mechanics, and administrative requirements. By using a structured checklist—verifying authorization rules, obtaining itemized estimates, and confirming settlement timelines—you can make decisions that are consistent, auditable, and aligned with professional operational standards.
Ultimately, the “meaning” of the phrase is not the brand label plus the locality keyword. The real meaning is what your specific plan contract says, what your provider is authorized to bill under that contract, how the authorization and documentation workflow is executed, and how settlement and disputes are handled when reality differs from expectations. When you verify those components, “Alelo Barueri” becomes less of a search term and more of an operational pathway you can confidently navigate.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

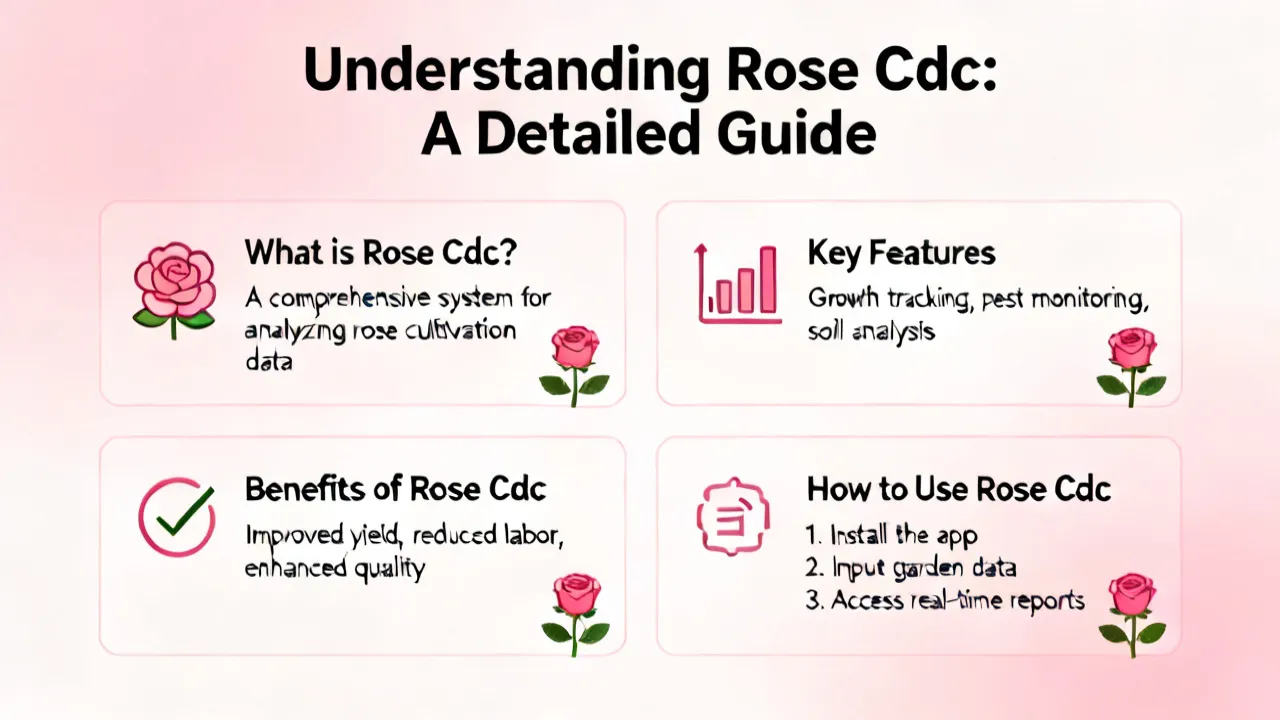
Understanding Rose Cdc: A Comprehensive Guide
This article provides an in-depth exploration of Rose Cdc, a term rapidly gaining attention in specific industries. Our discussion delves into the significance and application of Rose Cdc, its potential impact on various sectors, and expert insights into its future developments. This comprehensive analysis is designed to inform readers about the multifaceted aspects of Rose Cdc, its current applications, and potential advancements.

Understanding Compliance and AML Strategies
This article delves into the intricate realm of Compliance and Anti-Money Laundering (AML) strategies, highlighting their significance in the corporate world. Compliance AML refers to the organizational adherence to legal standards and regulations to deter financial crimes, ensuring transparent and ethical financial practices. This comprehensive guide examines these strategies' complexities and their pivotal role in safeguarding economic integrity.

Mastering Inbound B2B Strategies
The foundation of successful B2B strategies often lies in the effective implementation of inbound marketing techniques. In today's globally connected business environment, inbound B2B strategies have become critical for companies seeking to engage target audiences, optimize lead generation, and establish long-lasting partnerships. Understanding these strategies is essential for companies aiming to thrive in competitive markets.

Exploring B2B MBA Opportunities
Dive into the dynamic world of B2B MBA programs, designed for professionals seeking to enhance their strategic and management skills in a business-to-business context. This comprehensive guide discusses the significance of B2B MBAs in today's market, highlighting how these programs equip leaders with the expertise to navigate complex B2B relationships and drive business success.
Understanding Whitewater Regenerative Blowers
Whitewater Regenerative Blowers are essential in various industrial applications for their efficiency in moving air and gases. These blowers are known for their durability and ability to operate continuously, making them a preferred choice for industries ranging from wastewater treatment to aquaculture. This article explores their features, benefits, and applications, offering readers a comprehensive understanding of their importance in modern industry.

Mastering Employee Retention Strategies
Employee retention has become a critical aspect of organizational success, particularly in the dynamic landscape of 2020. As businesses strive to maintain a stable and productive workforce, understanding effective retention strategies is essential. This article delves into key methods for enhancing employee satisfaction and retention, offering a comprehensive guide for HR professionals and business leaders alike.
